D3.1 Reproduction
Reproduction covers cloning, human and plant reproductive anatomy, cycles, fertilization, pregnancy, seed development and hormonal coordination across sexual life cycles.
- Syllabus
- First assessment 2025
- Topic
- D3.1
- Level
- HL
Reproduction covers cloning, human and plant reproductive anatomy, cycles, fertilization, pregnancy, seed development and hormonal coordination across sexual life cycles.
| Feature | Asexual reproduction | Sexual reproduction |
|---|---|---|
| gametes and fertilization | absent | present |
| main nuclear divisions | mitosis | meiosis makes gametes; mitosis grows offspring |
| parentage | usually one parent | genetic contribution from two gametes |
| genetic outcome | clones, except for new mutations | new allele combinations |
Asexual reproduction can increase numbers rapidly when a successful genotype suits stable conditions. Sexual reproduction is slower and depends on gamete transfer, but variation increases the chance that some offspring suit changed conditions.
Clones are not guaranteed to remain absolutely identical: mutation and environmental effects can still create differences.
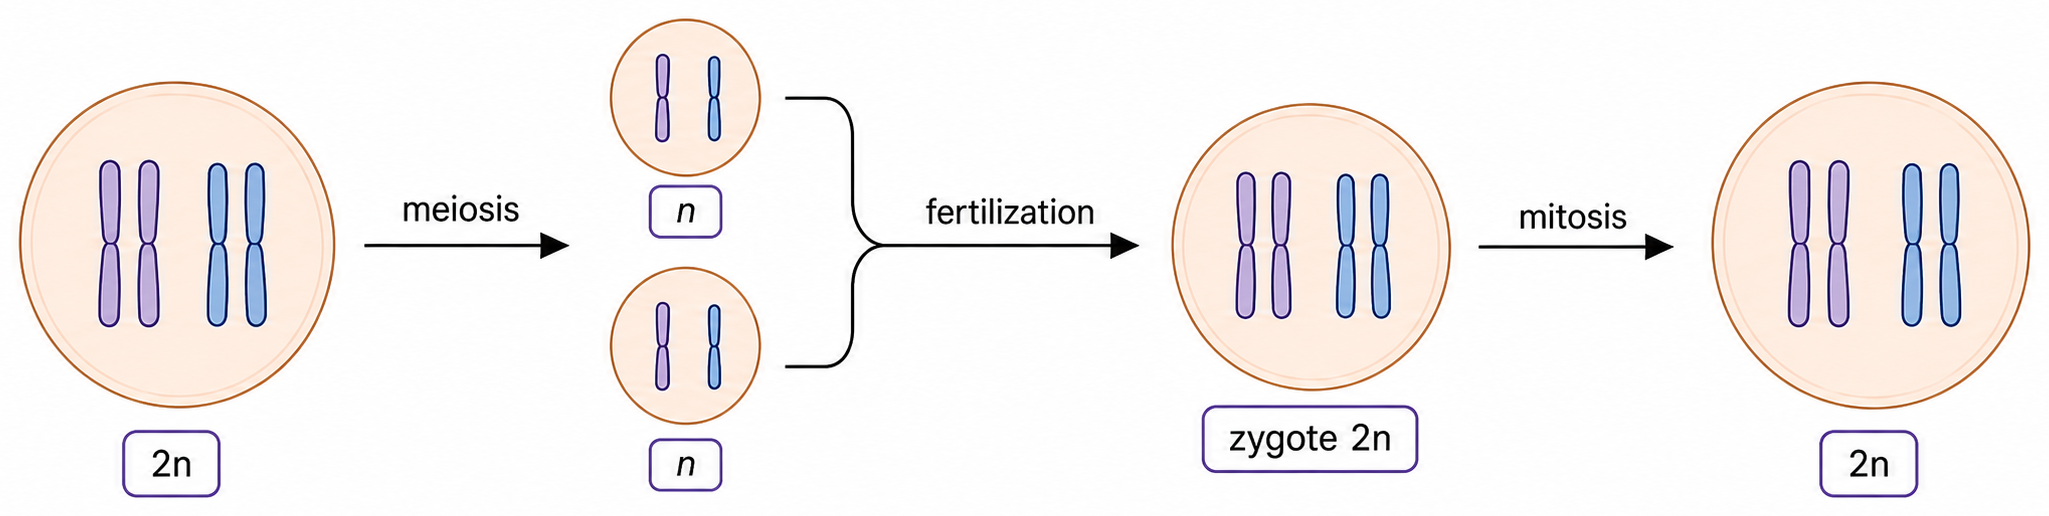
diploid germ cell (2n) → meiosis → haploid gametes (n) → fertilization → diploid zygote (2n) → mitosis → multicellular diploid organism
Meiosis halves the chromosome-set number before gametes fuse. Fertilization then adds one haploid set from each gamete, restoring diploidy rather than doubling the species' chromosome number every generation.
Haploid means one chromosome set and diploid means two sets. The human counts 23 and 46 are examples, not definitions for every species.
| Event | What is randomized | Result |
|---|---|---|
| crossing over in meiosis I | DNA segments exchanged between homologous non-sister chromatids | recombinant chromatids |
| independent assortment | maternal and paternal homologues sent to gametes in different combinations | many chromosome combinations |
| random fertilization | which genetically distinct sperm and egg fuse | a unique zygote combination |
Meiosis creates genetically varied haploid gametes; fertilization combines two of those independently varied genomes. Mutation can add new alleles, but recombination mainly rearranges alleles already present in the parents.
Variation is a population advantage under changing conditions, not a promise that every individual offspring will be better adapted.
In anisogamous species, the sex producing small gametes is defined as male and the sex producing large gametes as female.
| Gamete feature | Sperm / male gamete | Egg / female gamete |
|---|---|---|
| size | small | large |
| number produced | very many | relatively few |
| usual movement | motile or carried to the egg | usually non-motile |
| cytoplasm and reserves | little | abundant, supporting early development |
| shared requirement | haploid nucleus capable of fusion | haploid nucleus capable of fusion |
Producing many small gametes increases the chance that at least one reaches an egg. Investing more cytoplasm and resources in each egg supports the zygote before it can obtain resources independently.
Sex is defined here by gamete type, not by stereotypes about whole-organism behaviour or parental care.
seminiferous tubules in testes → epididymis → sperm duct → fluids added by seminal vesicles and prostate → urethra → penis
| Structure | Essential function |
|---|---|
| testes in scrotum | make sperm and testosterone at a temperature below body core |
| epididymis | completes sperm maturation and stores sperm |
| sperm duct | transports sperm during ejaculation |
| seminal vesicles and prostate | add nutrient-containing, alkaline seminal fluid |
| urethra and penis | conduct and deliver semen outside the body |
Semen is sperm plus glandular fluid. It is not produced entirely in the testes, and semen production is not the same process as spermatogenesis.
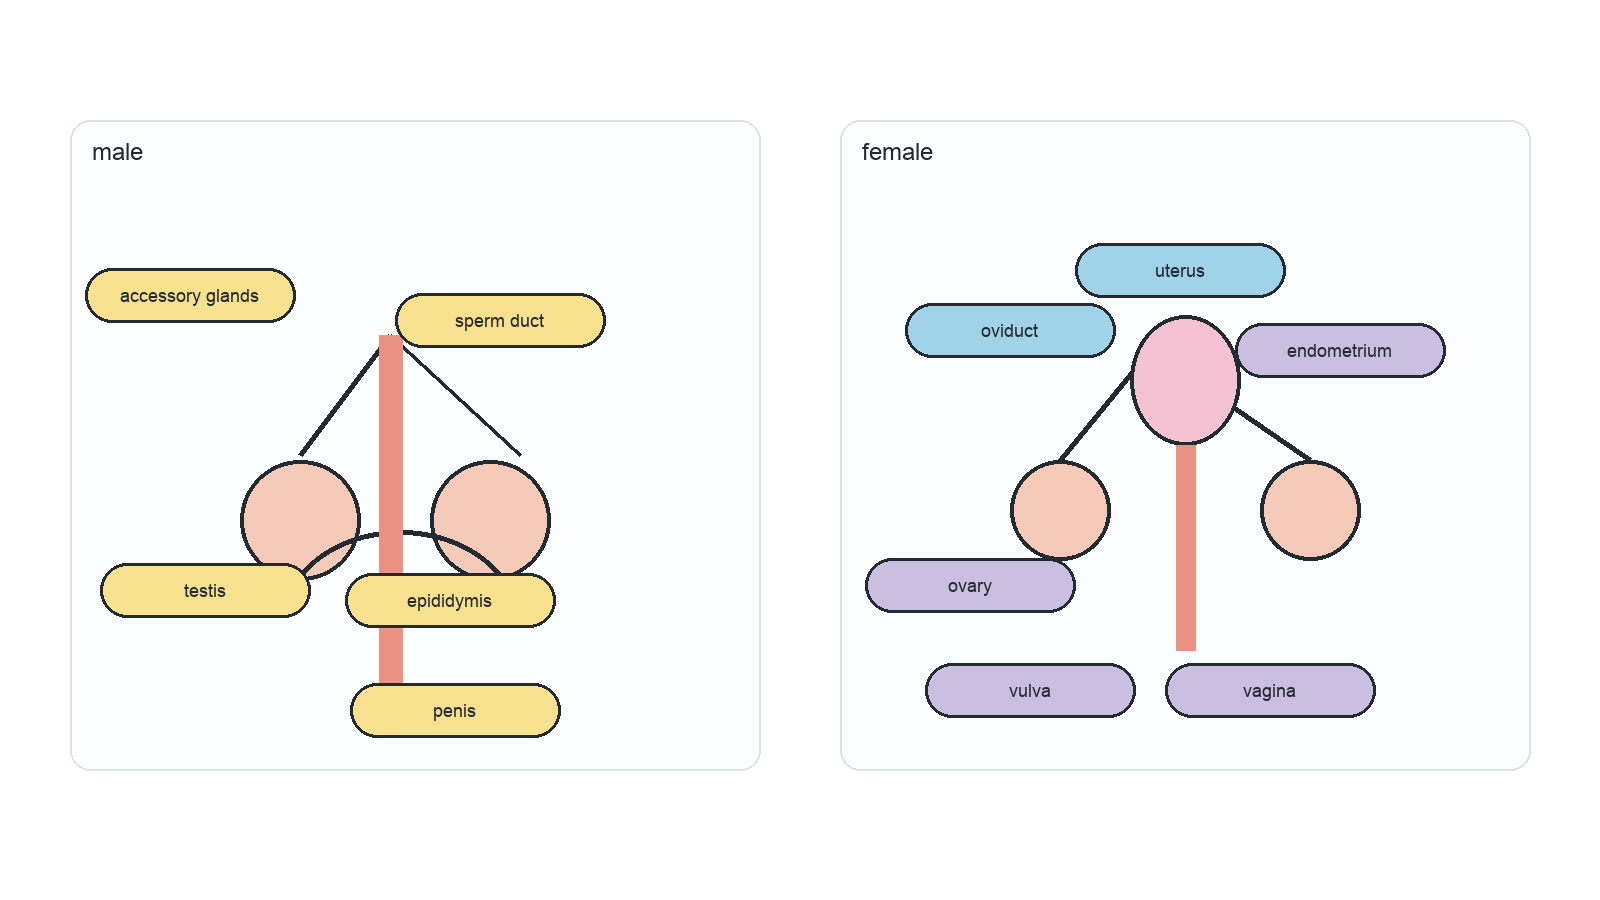
ovary releases secondary oocyte → oviduct receives and transports it; fertilization usually occurs in the upper oviduct → embryo reaches uterus → implantation occurs in endometrium → cervix and vagina form the exit route at birth
| Structure | Essential function |
|---|---|
| ovary | produces oocytes, oestradiol and progesterone |
| oviduct | transports oocyte or embryo; usual fertilization site |
| uterus | muscular organ supporting embryo and foetus |
| endometrium | vascular lining for implantation and early support |
| cervix | muscular neck between uterus and vagina |
| vagina and vulva | canal and external structures for intercourse and birth |
Draw the oviduct opening into the uterine cavity, not ending inside the uterine wall. The ovary lies near the funnel-shaped end but is not directly joined by a sealed tube.
| Approximate time | Ovary | Dominant signal | Endometrium |
|---|---|---|---|
| days 1–5 | new follicles begin developing | FSH rises | menstruation |
| days 5–13 | one follicle becomes dominant | rising oestradiol | rebuilds |
| around day 14 | ovulation | LH surge | remains prepared |
| days 15–28 | corpus luteum active, then degenerates if no pregnancy | progesterone rises, then falls | maintained, then shed |
Twenty-eight days and day 14 are useful averages, not fixed dates for every person or every cycle. Interpret event order and hormone relationships before relying on a calendar number.
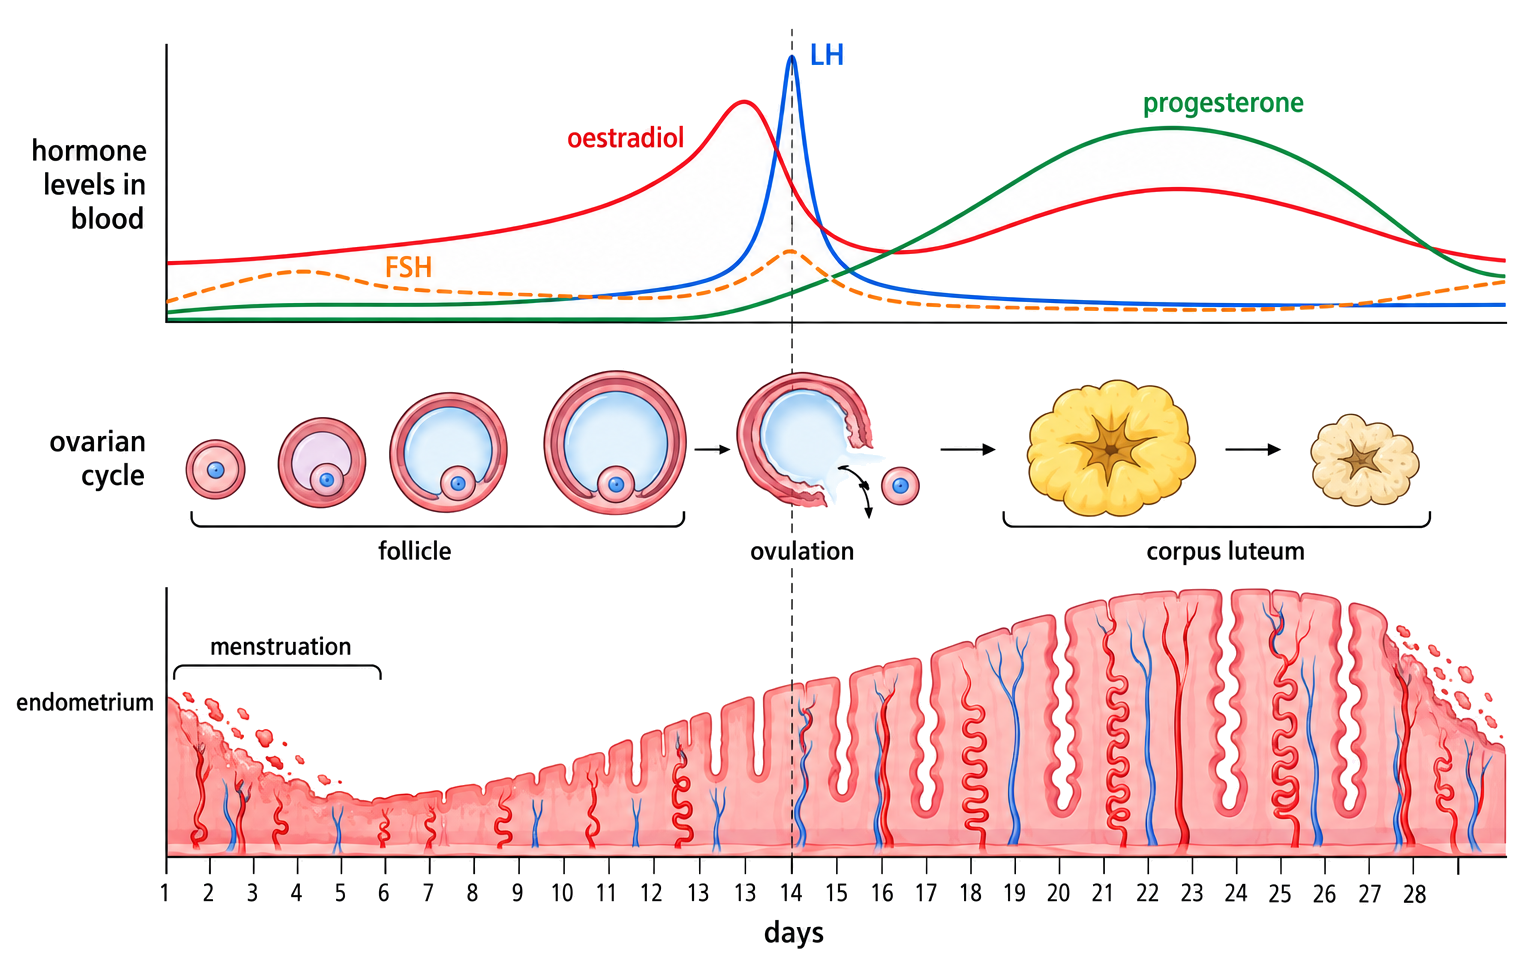
FSH from anterior pituitary → follicle growth → follicle secretes oestradiol → endometrium proliferates
| Oestradiol condition | Feedback effect | Functional consequence |
|---|---|---|
| rising during follicle development | supports further follicle responsiveness and oestradiol production | one follicle becomes dominant |
| high before mid-cycle | suppresses FSH but stimulates strong LH release | limits additional follicles and prepares ovulation |
FSH primarily stimulates follicle development. LH is not a substitute name for FSH; its surge triggers the later ovulation transition.
high oestradiol → LH surge → ovulation → ruptured follicle becomes corpus luteum
corpus luteum → progesterone plus oestradiol → endometrium maintained and FSH/LH inhibited
If pregnancy does not begin: corpus luteum degenerates → progesterone and oestradiol fall → endometrium is no longer maintained → menstruation; loss of inhibition allows FSH to rise for a new cycle.
Ovulation is caused by the LH surge. Menstruation is caused later by loss of ovarian steroid support; the two events are not simultaneous.
Human fertilization normally begins in the upper oviduct when a sperm reaches the secondary oocyte and their plasma membranes fuse.
sperm reaches and penetrates oocyte coverings → sperm and oocyte membranes fuse → sperm nucleus enters while most sperm mitochondria and tail remain outside → oocyte completes meiosis II → male and female haploid nuclear material forms the diploid zygote genome
The zygote receives one homolog of each chromosome pair from each parent. Nearly all cytoplasmic organelles, including mitochondria, come from the egg.
Fertilization occurs in the oviduct; implantation occurs later in the uterus. These are separate events at different locations.
Control and stimulation: suppress the natural cycle when the protocol requires it → inject FSH to develop multiple follicles → give an hCG trigger to coordinate final oocyte maturation.
Collection and culture: retrieve oocytes → combine with prepared sperm or inject one sperm → culture fertilized embryos and assess early development.
Transfer and support: place selected embryo or embryos in the uterus → provide progesterone support to maintain a receptive endometrium → test for pregnancy.
Transferring more embryos can increase the chance that one implants but also increases multiple-pregnancy risk. Modern protocols balance success with maternal and foetal safety.
meiosis halves chromosome-set number and reshuffles alleles → specialized haploid gametes form → random fertilization restores diploidy → mitosis grows the genetically unique zygote
| Transition | Main location | Key control or structure |
|---|---|---|
| sperm production and maturation | testis → epididymis | FSH/testosterone; seminiferous tubules |
| follicle growth and ovulation | ovary | FSH, oestradiol and LH surge |
| fertilization | upper oviduct | gamete encounter and membrane fusion |
| implantation preparation | endometrium | oestradiol and progesterone |
| IVF intervention | clinic/laboratory → uterus | controlled stimulation, retrieval, culture and transfer |
When explaining a reproductive event, name the chromosome state, the anatomical location and the controlling signal. Mixing these three levels is the main source of fragmented answers.
pollen transferred from anther to receptive stigma (pollination) → compatible pollen germinates → pollen tube grows through style → male nuclei enter ovule through micropyle → one male nucleus fuses with egg nucleus (fertilization) → diploid zygote develops into embryo
| Before fertilization | After fertilization |
|---|---|
| ovule contains female gamete | ovule develops into seed |
| ovary contains one or more ovules | ovary develops into fruit |
| egg nucleus is haploid | zygote nucleus is diploid |
Pollination ends at the stigma. Pollen does not travel intact to the ovary; a pollen tube carries male nuclei from the stigma through the style.
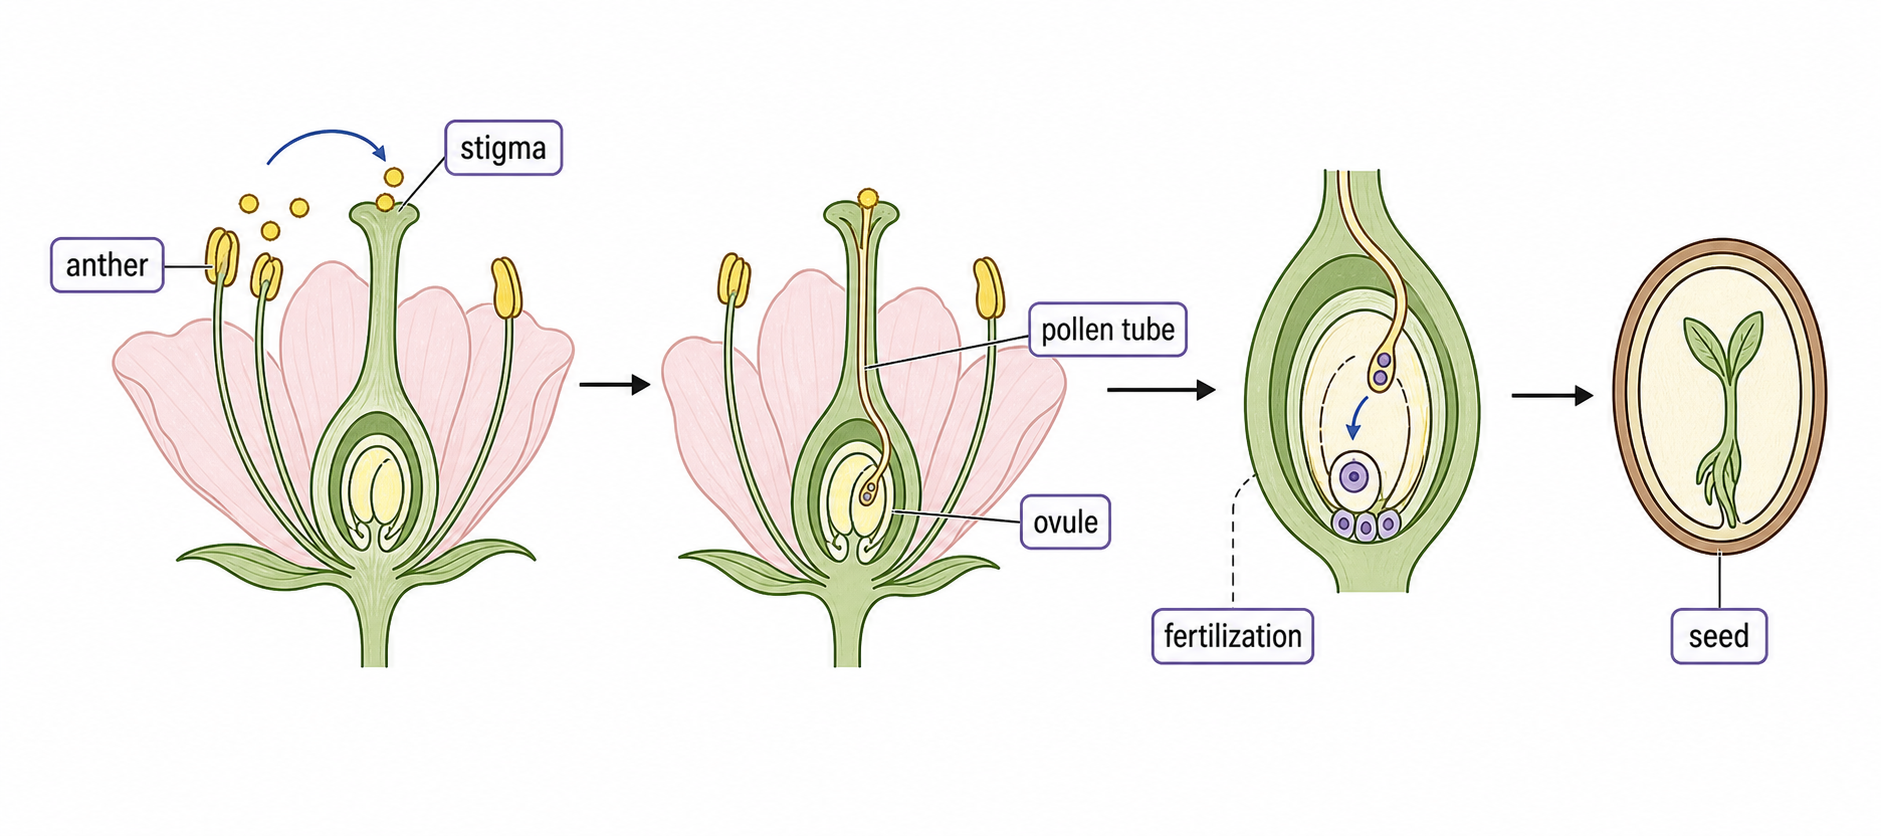
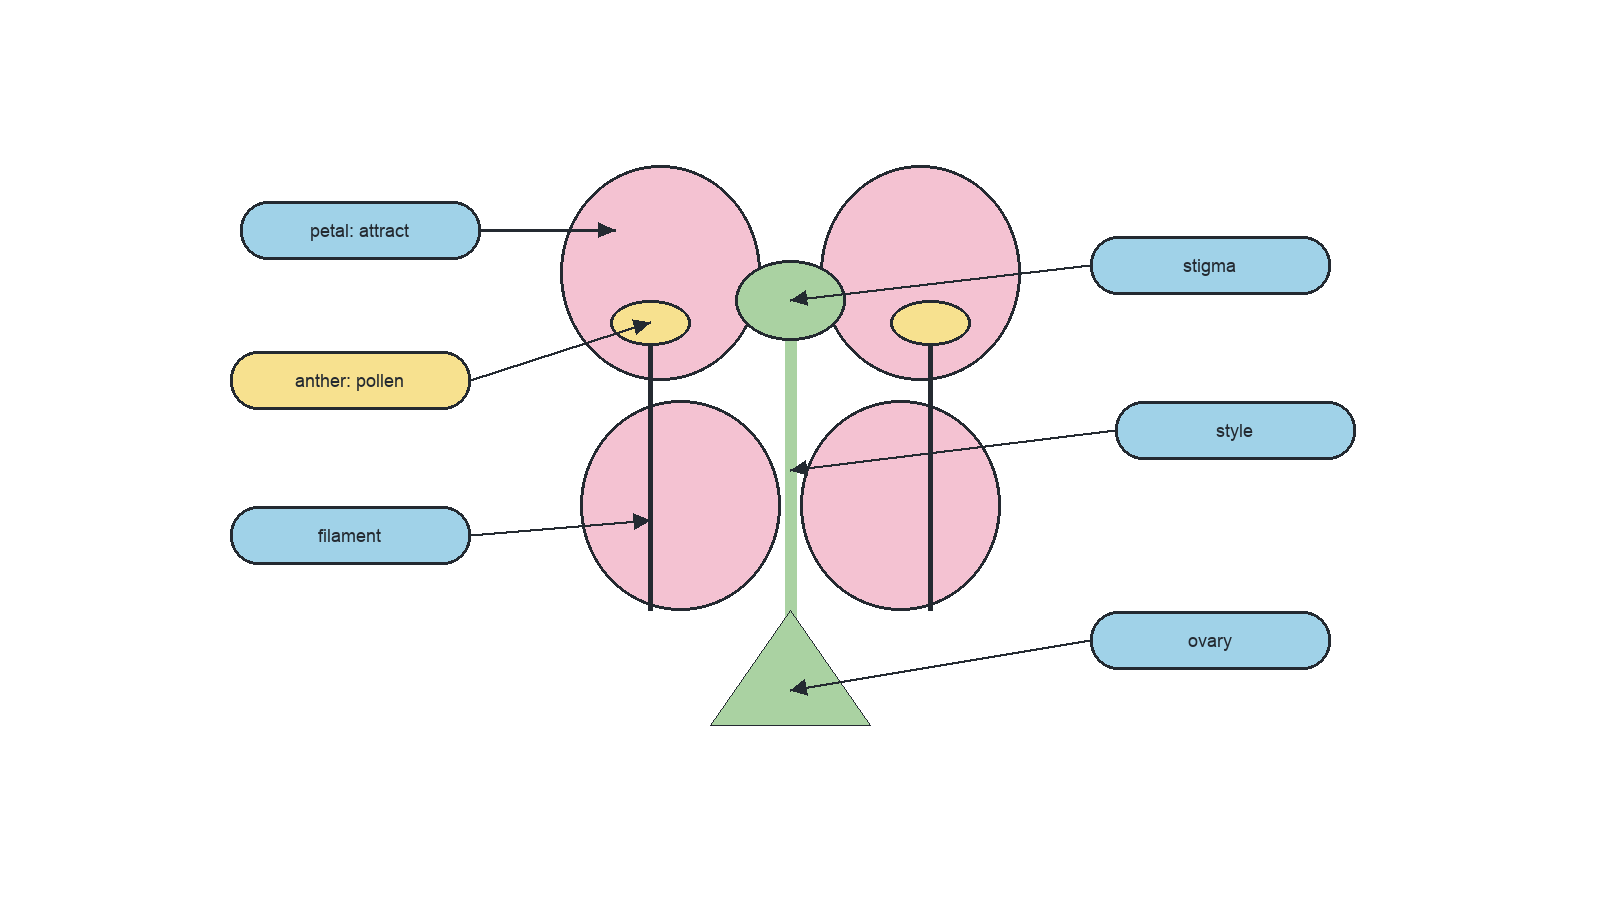
| Whorl or organ | Parts | Reproductive function |
|---|---|---|
| sepals | calyx | protect the developing flower bud |
| petals | corolla | advertise to animal pollinators |
| stamen | anther + filament | produce and present pollen |
| carpel | stigma + style + ovary | receive pollen, guide tube and contain ovules |
Anther produces pollen → filament presents anther → stigma receives pollen → style provides pollen-tube path → ovary contains ovules where fertilization occurs.
| Feature | Effect on pollination |
|---|---|
| conspicuous petals and scent | attract insects from a distance |
| nectar | rewards entry and repeated visits |
| anthers placed on the route | dust visiting insect with pollen |
| sticky or sculptured pollen | adheres to animal body |
| stigma placed on the route | contacts pollen carried from another flower |
| sticky stigma | retains deposited pollen |
The features work as a system: attraction brings the insect, reward draws it into a predictable position, and flower geometry makes its body contact anthers or stigmas.
The plant gains gamete transfer; the pollinator gains nectar or pollen food. This mutualism increases transfer efficiency but does not guarantee that every visit causes cross-pollination.
Cross-pollination transfers pollen from an anther on one plant to a stigma on a different plant of the same species, increasing opportunities to combine different parental alleles.
| Mechanism | How self-pollination is reduced |
|---|---|
| anthers and stigma mature at different times | self-pollen is absent when the stigma is receptive |
| anthers and stigma are at different heights | a visitor contacts them on different body regions |
| separate male and female flowers or plants | one flower or plant cannot supply both gametes |
| pollinator movement or wind | carries pollen between individuals |
Cross-pollination can increase genetic variation, but it also depends on pollen reaching a compatible plant. The mechanism reduces selfing; it does not ensure successful fertilization.
Self-incompatibility is a genetically controlled recognition system in which a carpel rejects pollen carrying an incompatible self identity.
pollen lands on stigma → pollen and carpel recognition alleles or proteins are compared → incompatible self pollen fails to hydrate, germinate or extend its tube → male nucleus cannot reach ovule → self-fertilization is prevented
Rejecting genetically similar pollen promotes outcrossing, reduces inbreeding and lowers the chance that identical harmful recessive alleles meet in offspring.
Self-incompatibility acts after pollen arrives. It is different from temporal or spatial separation, which reduces the chance that self pollen reaches the stigma.
| Flower structure | Mature product |
|---|---|
| zygote | embryo root, shoot and cotyledon or cotyledons |
| fertilized ovule | seed containing embryo and food reserve |
| ovule wall | protective seed coat or testa |
| ovary | fruit surrounding or carrying seeds |
Wind, water, animals or explosive fruit mechanisms carry seeds away from the parent. Separation reduces competition for light, water, minerals and space and can colonize new sites.
Pollination moves pollen before fertilization. Seed dispersal moves a fertilized, developing offspring after seed formation.
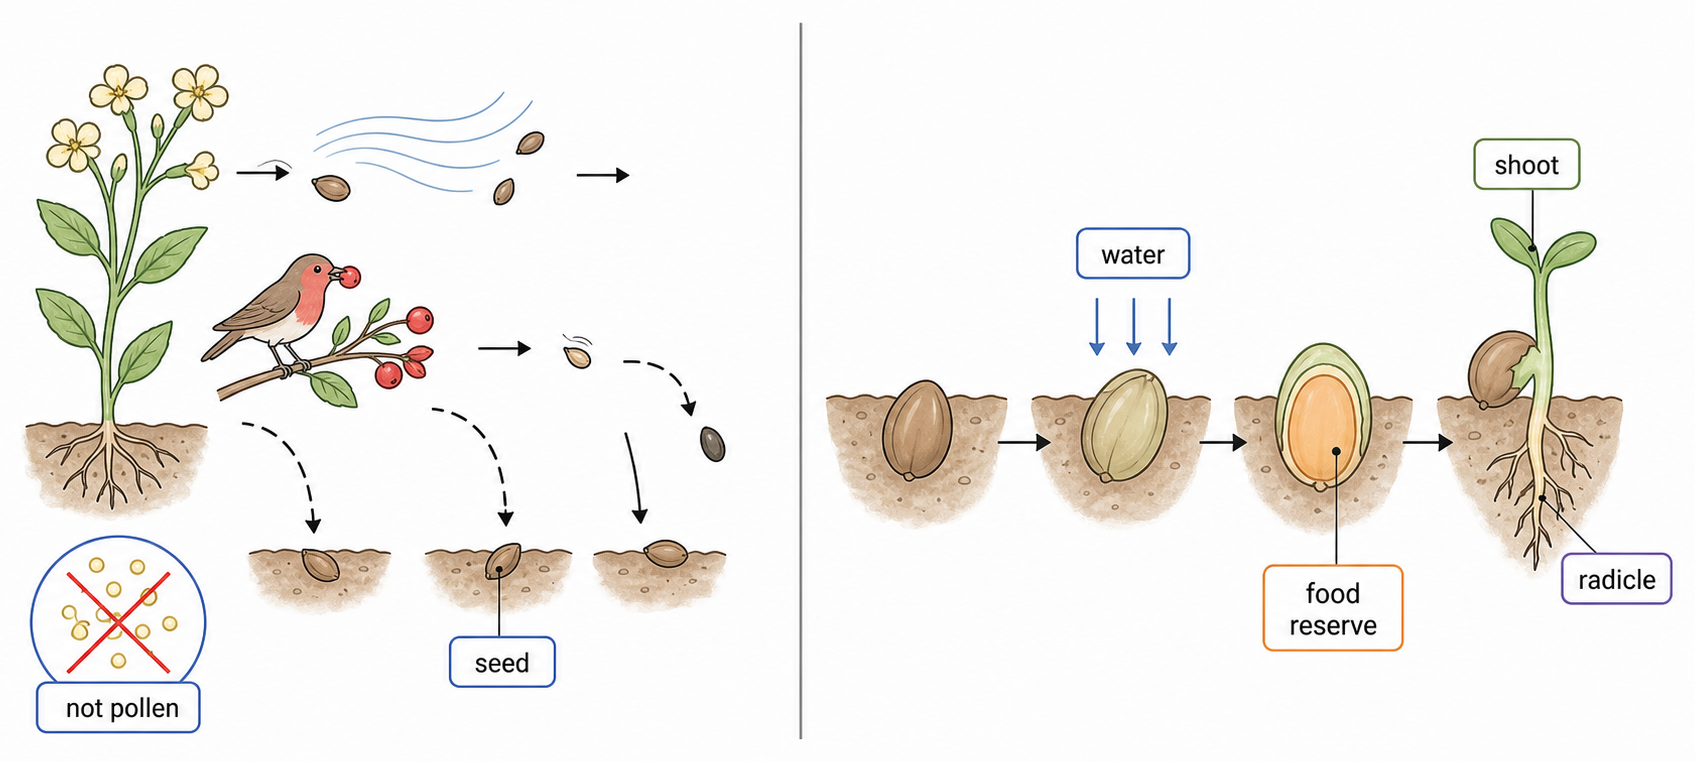
Dormancy is an internal block to growth in a viable seed; germination is the resumed growth of the embryo using stored food.
Dormancy may persist because the embryo is immature, inhibitory abscisic acid remains, the testa is impermeable, or a species-specific chilling period has not occurred.
| External condition | Why germination needs it |
|---|---|
| water | rehydrates cells, softens testa and enables metabolic reactions |
| oxygen | supports aerobic respiration and ATP production |
| suitable temperature | permits enzyme-catalysed reserve mobilization and growth |
Light is required for germination in some species but not all. Water, oxygen and a suitable temperature are the general conditions emphasized here.
water uptake activates embryo → embryo releases gibberellin → signal reaches food-storage tissue → hydrolytic enzymes such as amylase are produced → starch becomes maltose and then glucose; proteins become amino acids → soluble products move to growing root and shoot
| Mobilized product | Immediate use |
|---|---|
| glucose | respiration for ATP and carbon skeletons for biosynthesis |
| amino acids | synthesis of enzymes and structural proteins |
The seedling depends on stored reserves until leaves expand and photosynthesis supplies enough organic material for independent growth.
pollen production → transfer to stigma → compatibility check → pollen-tube delivery → gamete fusion in ovule → seed and fruit formation → dispersal → dormancy release → germination and reserve mobilization
| Transition problem | Adaptation |
|---|---|
| pollen must reach a conspecific stigma | pollinator attraction, wind transfer and flower geometry |
| selfing can reduce variation | timing, spatial separation, separate sexes and self-incompatibility |
| offspring compete with parent | seed dispersal |
| growth begins in poor conditions | dormancy and environmental germination requirements |
Pollination is gamete delivery, fertilization is nuclear fusion, and dispersal moves the resulting seed. Keep those transitions separate while explaining how each supports successful outcrossing and establishment.
hypothalamus increases pulsatile GnRH → anterior pituitary releases FSH and LH → gonads increase gametogenesis and steroid-hormone secretion → reproductive organs mature and secondary sexual characteristics develop
| Shared level | Testis-dominant response | Ovary-dominant response |
|---|---|---|
| pituitary gonadotropins | FSH supports sperm production; LH stimulates testosterone secretion | FSH supports follicle development; LH supports ovulation and ovarian steroid secretion |
| gonadal steroids | testosterone supports reproductive maturation and male-typical secondary traits | oestradiol and progesterone support reproductive maturation and female-typical cyclic changes |
Sex steroids also influence bone growth, muscle protein synthesis and changes in body composition. Puberty is therefore a coordinated endocrine transition, not a single anatomical event.
FSH and LH operate in all sexes; their names reflect how they were first studied, not hormones found only in ovaries.
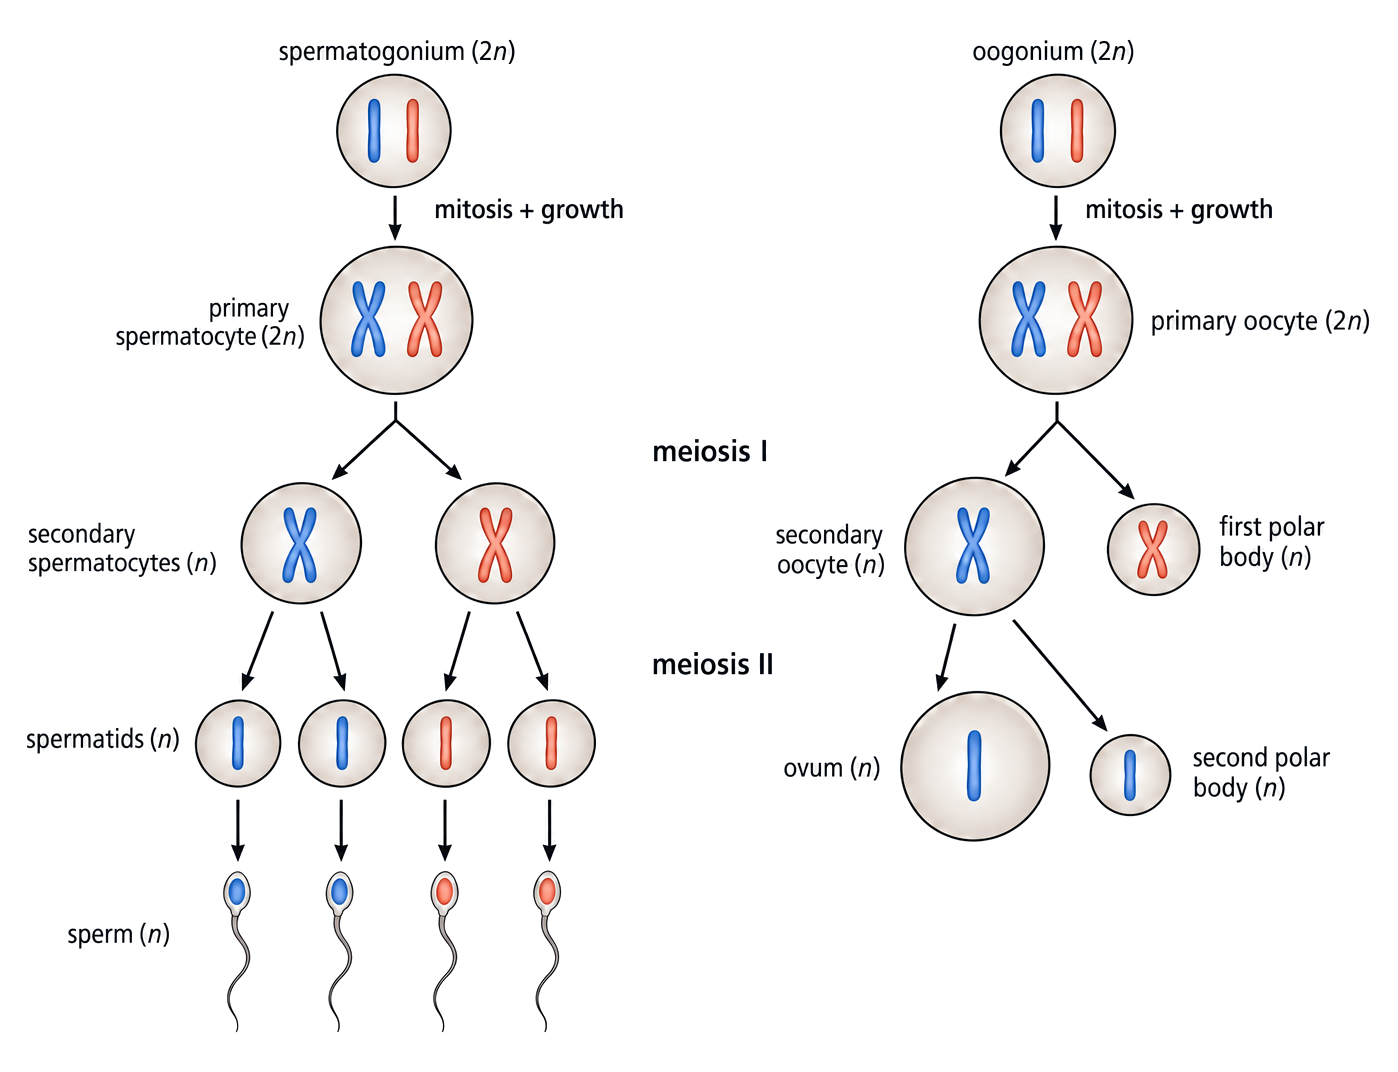
Spermatogenesis begins at puberty in the germinal epithelium of seminiferous tubules and continues toward the tubule lumen with support from Sertoli cells.
| Cell stage | Division or change | Ploidy / product |
|---|---|---|
| spermatogonium | mitosis and growth | primary spermatocyte, 2n |
| primary spermatocyte | meiosis I | two secondary spermatocytes, n |
| secondary spermatocytes | meiosis II | four spermatids, n |
| spermatids | differentiation, no further division | four mature sperm, n |
Sertoli cells nourish and organize developing germ cells. Interstitial cells between tubules secrete testosterone; the epididymis completes sperm maturation and stores the cells after they leave the testis.
Spermatids are the products of meiosis; sperm are the differentiated cells. Adding seminal-vesicle and prostate fluid later produces semen, not more sperm.
Oogenesis begins before birth. Primary oocytes remain arrested in follicles until cycles after puberty recruit a small group for further development.
oogonium divides by mitosis and grows → primary oocyte begins meiosis → meiosis I completes with unequal cytokinesis → large secondary oocyte plus first polar body → secondary oocyte begins meiosis II and is ovulated while arrested → sperm entry triggers completion → ovum plus second polar body
Unequal cytokinesis keeps almost all cytoplasm, organelles and stored materials in one cell while polar bodies remove extra chromosome sets. The products are genetically haploid but not equal in developmental capacity.
The cell released at ovulation is normally a secondary oocyte, not yet a completed ovum. Meiosis II finishes only if fertilization begins.
| Dimension | Spermatogenesis | Oogenesis |
|---|---|---|
| begins | puberty | before birth, resumes after puberty |
| production pattern | continuous after puberty | cyclic recruitment from finite primary-oocyte pool |
| cytokinesis | approximately equal | highly unequal |
| products per primary cell | four functional sperm | one functional ovum plus polar bodies |
| meiosis II | completes before sperm differentiation | completes only after sperm entry |
Both begin with diploid germ cells, include a multiplication and growth phase, use meiosis I to separate homologues and meiosis II to separate sister chromatids, and produce haploid nuclei.
The contrast explains anisogamy: sperm production maximizes the number of motile gametes, whereas oogenesis concentrates resources into one large cell capable of supporting the earliest embryo.
GnRH → pituitary FSH and LH → gonadal steroid secretion plus gametogenesis → sexually mature reproductive systems
| Question | Sperm route | Oocyte route |
|---|---|---|
| where? | seminiferous tubules | ovarian follicles |
| when? | continuous from puberty | begins before birth; resumes cyclically |
| how many functional products? | four per primary spermatocyte | one per primary oocyte |
| why different? | maximize delivery probability | concentrate cytoplasm and reserves |
Track cell name, chromosome-set number, cytoplasm and timing together. Those four dimensions distinguish the routes more reliably than memorizing isolated stage lists.
sperm passes between follicle cells → sperm surface interacts with zona pellucida → acrosomal membrane releases hydrolytic enzymes → enzymes digest a local path through zona → sperm reaches and fuses with oocyte plasma membrane
The acrosome is a membrane-bound enzyme compartment at the sperm head. Its reaction is localized: it enables one sperm to cross the extracellular coat rather than dissolving the entire zona pellucida.
The acrosome reaction permits penetration. It does not itself prevent polyspermy; the block is triggered after sperm–oocyte membrane fusion.
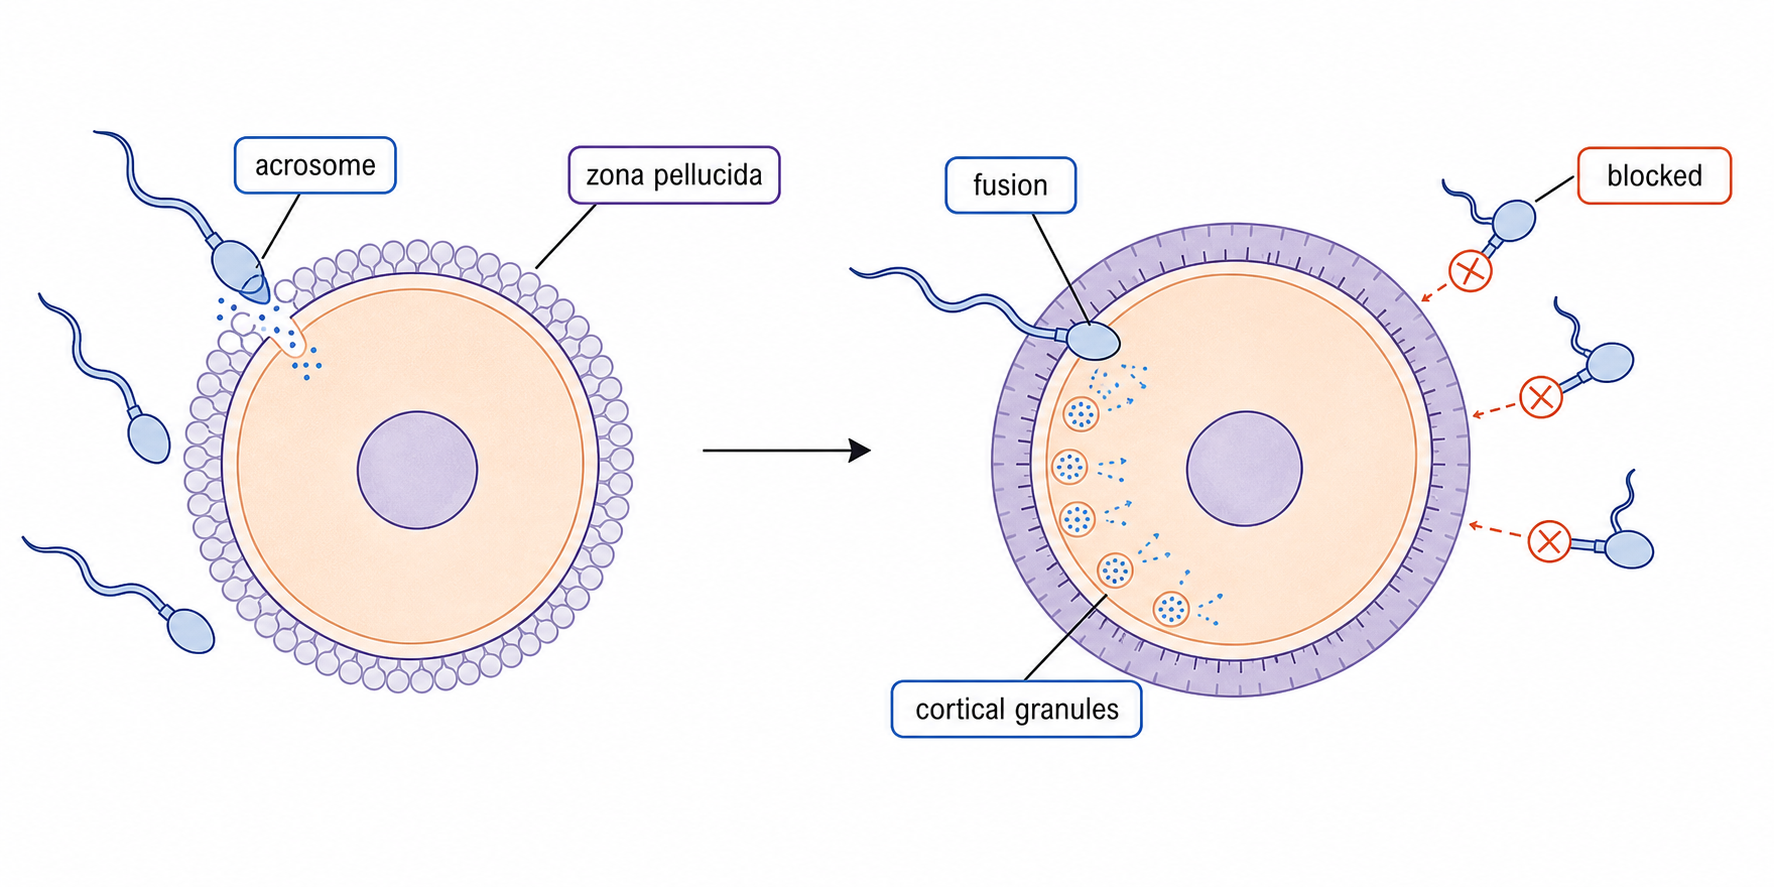
Fusion of the first sperm and oocyte plasma membranes triggers a rapid calcium-mediated release of cortical-granule contents by exocytosis.
first membrane fusion → cortical granules release enzymes outside oocyte → zona-pellucida proteins are modified and hardened → additional sperm can no longer bind or penetrate effectively → only one paternal nucleus enters
If two sperm nuclei fused with the oocyte nucleus, the zygote would receive an abnormal extra chromosome set. Blocking later sperm therefore protects the diploid chromosome complement required for normal development.
The block must follow the first successful fusion quickly. A barrier acting before any fusion would prevent fertilization altogether.
zygote → 2-cell and 4-cell cleavage stages → compact morula → fluid-filled blastocyst
During cleavage, repeated mitoses partition the original zygote cytoplasm into progressively smaller blastomeres. Cell number rises, but the embryo has not yet gained substantial mass.
Cilia and smooth-muscle activity move the dividing embryo down the oviduct so that blastocyst formation and uterine arrival are coordinated.
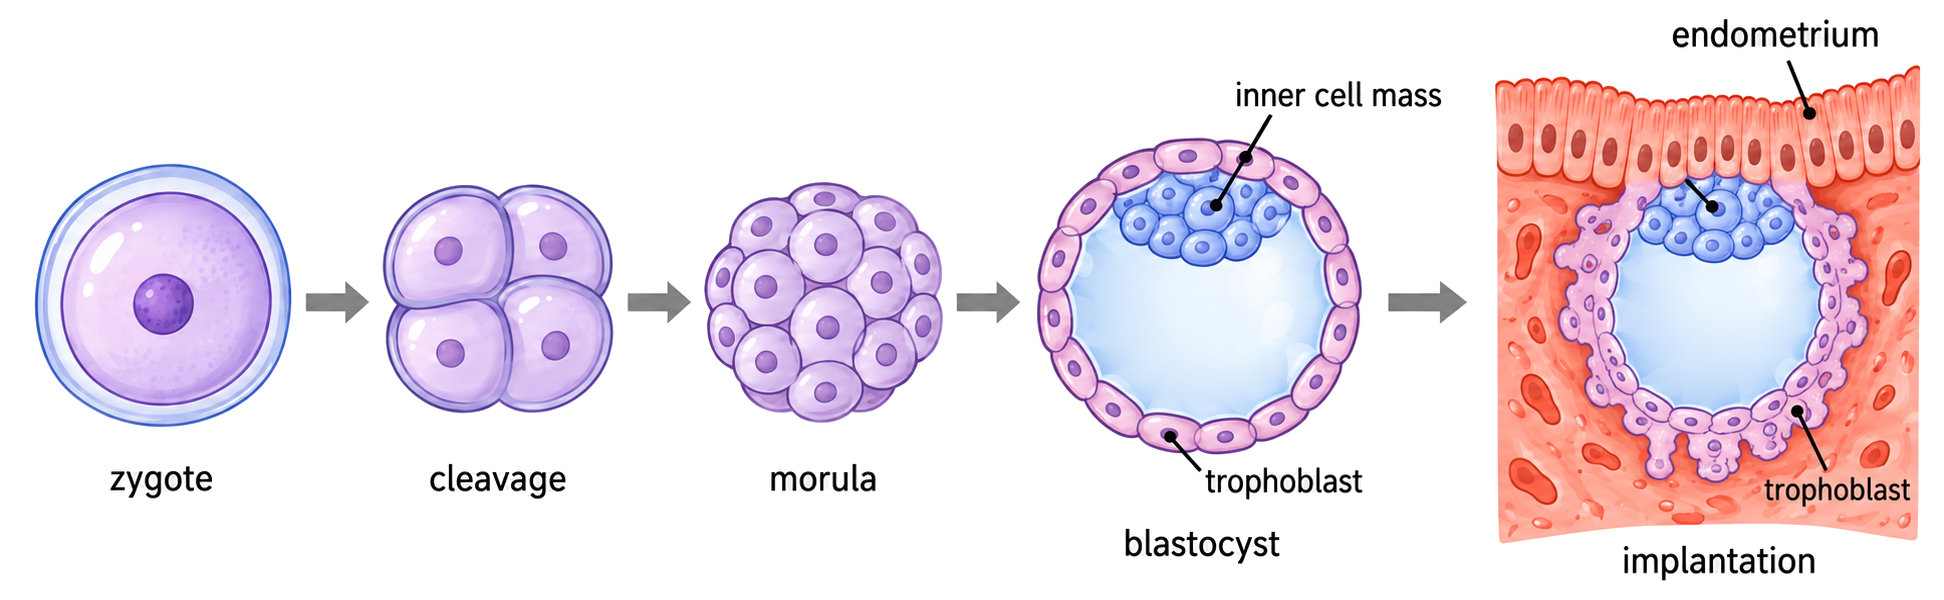
| Blastocyst region | Early role |
|---|---|
| inner cell mass | gives rise to the embryo proper and later foetus |
| outer trophoblast cells | attach to and invade endometrium; contribute to placenta |
| fluid-filled cavity | creates the blastocyst organization rather than a solid morula |
about day 7: blastocyst contacts receptive endometrium → trophoblast attaches and invades → embryo embeds over the following days → maternal tissue and embryonic membranes begin forming the placenta
Implantation anchors the embryo and establishes access to endometrial nutrients before the mature placental exchange system is complete.
The blastocyst is not simply a larger morula. Its cells have reorganized into an inner mass, outer layer and cavity with different developmental roles.
Without a pregnancy signal, the corpus luteum degenerates, progesterone falls and the endometrium is shed. An implanted embryo must interrupt that normal reset.
trophoblast / early placenta secretes hCG → hCG maintains corpus luteum → corpus luteum continues progesterone secretion → endometrium remains thick and vascular → early pregnancy is sustained
As the placenta develops, it becomes an endocrine organ and increasingly supplies progesterone and oestradiol itself, so pregnancy no longer depends on the corpus luteum indefinitely.
The signal must be produced early because the non-pregnant cycle is already programmed to reduce luteal hormone support.
A lateral-flow pregnancy test detects hCG in urine with specific monoclonal antibodies and produces separate test and control lines.
urine moves by capillary action → hCG binds mobile coloured anti-hCG antibody → complex is captured by immobilized antibody at test line → coloured test line appears
excess mobile coloured antibody continues along strip → a different immobilized antibody captures it at control line → coloured control line confirms that liquid flowed and reagents functioned
| Lines visible | Interpretation |
|---|---|
| control + test | hCG detected |
| control only | no hCG detected above test threshold |
| no control line | invalid test, regardless of test-line appearance |
| Placental feature | Exchange advantage |
|---|---|
| many branching villi and microvilli | large surface area |
| thin barrier between maternal blood space and foetal capillaries | short diffusion distance |
| continuous maternal and foetal blood flow | maintains concentration gradients |
| extensive foetal capillary network | rapidly carries exchanged substances away or toward surface |
Maternal blood bathes the outside of villi; foetal blood remains inside villus capillaries connected to the umbilical cord. Substances cross the placental barrier, but the blood cells normally do not mix.
Separation reduces immune and pressure incompatibilities while still permitting efficient molecular exchange across a small distance.
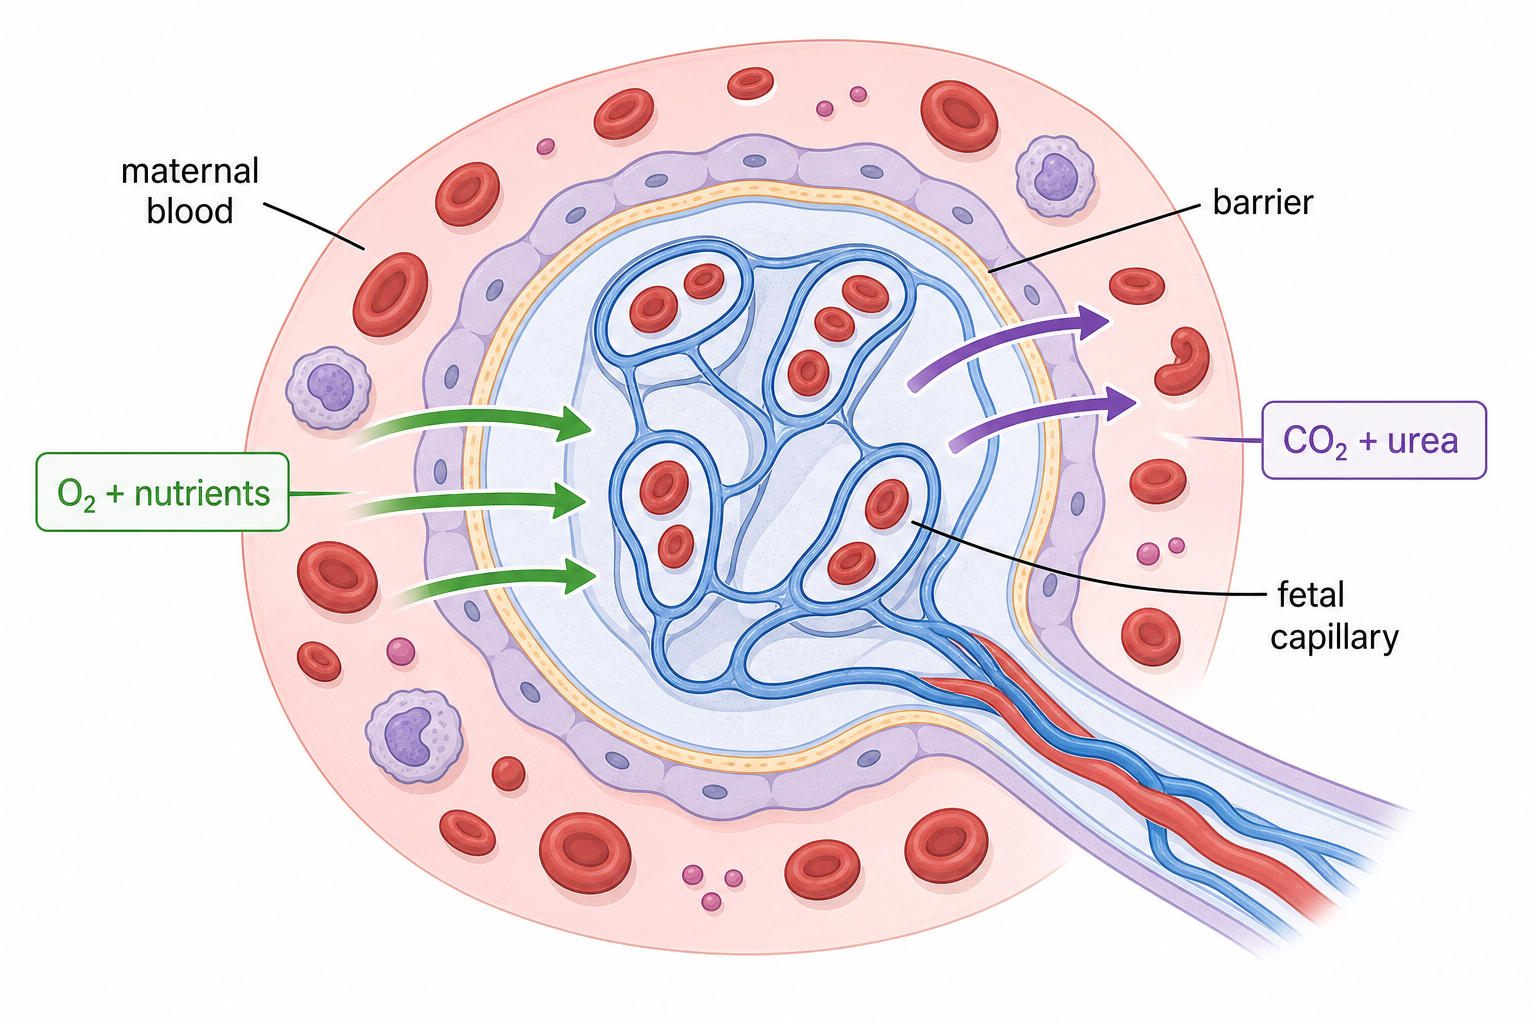
| Material | Main direction | Typical mechanism or significance |
|---|---|---|
| oxygen | mother → foetus | diffusion down maintained gradient |
| carbon dioxide | foetus → mother | diffusion |
| glucose | mother → foetus | facilitated diffusion |
| amino acids and some ions | mother → foetus | active transport contributes |
| water | both directions as gradients require | osmosis |
| urea and other wastes | foetus → mother | diffusion / transport for maternal excretion |
| maternal antibodies | mother → foetus | receptor-mediated transfer gives passive immunity |
The placenta is a selective exchange organ, not a perfect shield. Many bacteria are excluded, but some viruses, drugs, alcohol and other small molecules can cross and affect development.
The foetus does not breathe air or eat directly. Maternal respiratory, digestive and excretory systems supply and remove materials through the placental interface.
Early pregnancy: embryonic hCG maintains corpus luteum → corpus luteum secretes progesterone and oestradiol → endometrium remains intact.
Later pregnancy: placenta becomes main source of progesterone and oestradiol → uterine lining and pregnancy conditions continue after corpus luteum declines.
| Hormonal effect | Reproductive consequence |
|---|---|
| progesterone maintains endometrium and suppresses uterine contraction | implantation site remains supportive |
| progesterone and oestradiol inhibit FSH and LH | further follicle development and ovulation are suppressed |
The source changes from ovary to placenta, but hormone output overlaps so support is not interrupted during the handover.
Near birth, reduced progesterone influence removes inhibition of uterine muscle, allowing oxytocin and prostaglandins to promote coordinated contractions.
uterine contractions push foetal head against cervix → cervix stretches → sensory signals reach hypothalamus → posterior pituitary releases more oxytocin → contractions become stronger and more frequent → cervix stretches further
The loop is positive because each response strengthens the original stimulus. Birth removes the foetal head from the cervix, ending stretch and therefore breaking the loop.
Positive feedback is useful here because labour needs a decisive endpoint. It is not the usual stabilizing negative feedback used to maintain a physiological variable near a set point.
During menopause, ovarian responses and secretion of oestradiol and progesterone decline, menstrual cycles cease and loss of steroid-hormone effects can produce symptoms.
Hormone replacement therapy supplies oestradiol, with a progestogen when protection of an intact endometrium is required, to reduce symptoms such as hot flushes and other effects of hormone loss.
Benefit and risk depend on the individual, hormone formulation, dose, route, timing and duration. The biology course uses HRT to examine evidence, not to prescribe one treatment for everyone.
Replacing hormones can reduce symptoms without restoring fertility or reversing ovarian ageing.
| Study design | Observation | Main inference limit |
|---|---|---|
| early observational studies | HRT users had lower CHD incidence | users differed in socioeconomic status, health-service use and other risk factors |
| randomized controlled trials | treatment groups showed a small CHD-risk increase in the studied populations | result depends on participants, regimen and timing but better isolates treatment effect |
A confounding variable is associated with both the exposure and the outcome. Higher socioeconomic status could increase HRT uptake while independently lowering coronary risk, creating a protective-looking correlation.
To claim causation, ask whether groups were comparable before treatment, whether allocation was randomized, whether outcome measurement was blinded, and whether the effect is consistent with biological mechanism and other trials.
Correlation can motivate a hypothesis, but it cannot by itself show that HRT caused the lower—or higher—disease rate.
acrosome opens a local path → cortical reaction closes entry to later sperm → cleavage builds cell number → blastocyst opens an interface with endometrium → hCG keeps hormonal support open → placenta maintains selective exchange → oxytocin feedback drives birth to completion
| Transition | Enabling mechanism | Protective limit |
|---|---|---|
| fertilization | acrosomal penetration and membrane fusion | cortical polyspermy block |
| implantation | trophoblast attachment and invasion | organized endometrial interface |
| foetal exchange | thin, vascular placental villi | maternal and foetal blood remain separate |
| pregnancy to birth | progesterone support followed by oxytocin amplification | loop ends when cervical stretch ends |
| hormone therapy | replacement of lost signalling | evidence-based benefit–risk selection |
Successful reproduction is not one event. Each stage depends on a signal or structure that enables the next transition while preventing an incorrect place, time, cell or causal conclusion.
3 marks
Outline natural methods of cloning in some eukaryotes.
4 marks
Explain the need for both fusion of gametes and meiosis in a sexual life cycle.
6 marks
Draw a labeled diagram of the female reproductive system.
8 marks
Explain the roles of specific hormones in the menstrual cycle, including positive and negative feedback mechanisms.
6 marks
Describe the process of fertilization in humans.
9 marks
Embryos that are produced by in vitro fertilization can be screened for genetic disease. Outline the process of in vitro fertilization, including one example of a situation when it is used.
4 marks
Outline pollination, fertilization and seed dispersal.
4 marks
Draw a half-view of an animal-pollinated flower.
2 marks
Outline how cross-pollination can be promoted by flowering plants.
1 mark
Cherry trees (Prunus avium) have two self-incompatibility alleles. What benefit do self-incompatibility alleles have?
6 marks
Outline the metabolic processes that occur in starchy seeds during germination.
1 mark
What controls the developmental changes during puberty?
I. Increased release of gonadotropin-releasing hormone (GnRH) by the hypothalamus
II. Luteinizing hormone (LH) leading to increased sex hormone production
III. Gonadotropin-releasing hormone (GnRH) triggering the onset of increased luteinizing hormone (LH)
8 marks
Compare and contrast the processes of spermatogenesis and oogenesis.
2 marks
Explain the mechanism that prevents polyspermy during fertilization.
1 mark
What is a blastocyst?
1 mark
What is a function of human chorionic gonadotropin (HCG)?
8 marks
Explain how the structure and functions of the placenta maintain pregnancy.
7 marks
Describe the hormone feedback mechanisms that help to prepare a woman's body for pregnancy, sustain the pregnancy and then give birth.