Defence against disease combines physical barriers, clotting, phagocytes, lymphocyte specificity, vaccination, antibiotics and evolutionary responses to pathogens across human populations.
A Pathogen Starts an Infection; Damage Produces Disease
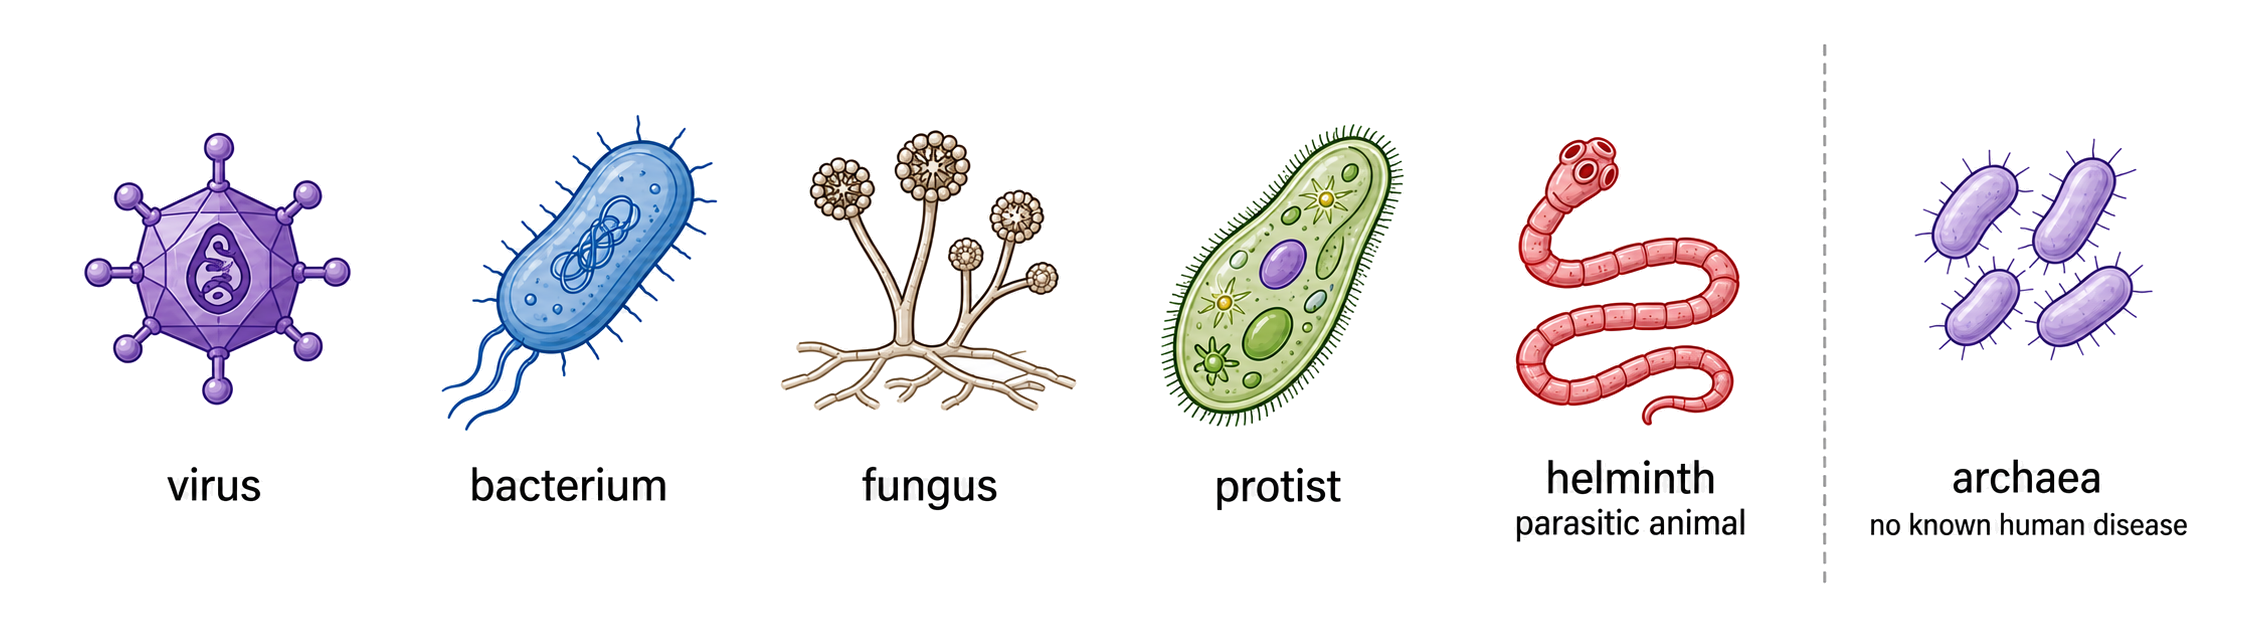
A pathogen is a disease-causing biological agent. Infection means that it has entered and established itself in a host; infectious disease is the harmful condition that can result.
Group
Disease-causing examples?
viruses, bacteria, fungi, protists
yes
parasitic animals, including helminths
yes
archaea
no human infectious disease is currently known
Viruses are pathogens but are not cells. Exposure also does not guarantee disease: entry, replication, host defence and tissue damage all affect the outcome.
Intact Skin Is a Layered Barrier
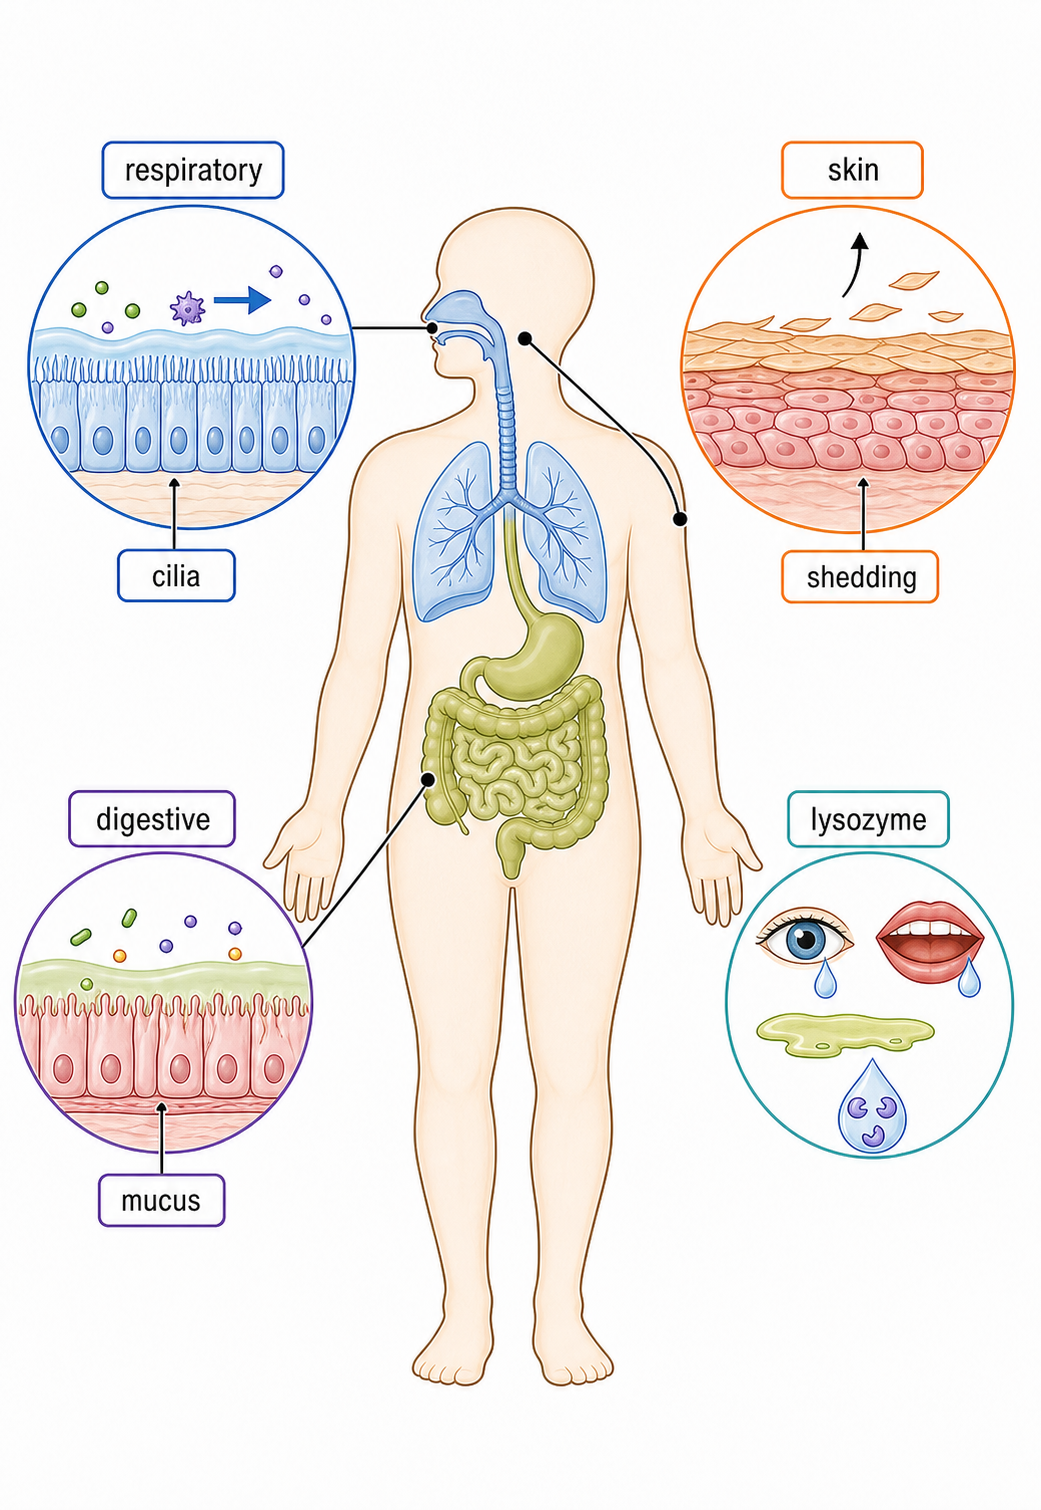
Keratinized cells form a tough, dry physical barrier.
Continuous shedding removes attached microbes.
Skin secretions create chemical conditions that inhibit many microbes.
A cut, bite or puncture bypasses this barrier. The defence is strongest while the surface remains intact.
Mucous Membranes Trap, Move and Damage Pathogens
Respiratory and digestive surfaces must exchange materials, so they cannot be sealed by thick dry skin. They use a trap-and-remove system instead.
Mechanism
Protective result
mucus
traps microbes and particles
cilia
sweep trapped material toward the throat
swallowing or coughing
removes material from the airway
lysozyme in tears, saliva and mucus
hydrolyses bacterial cell-wall peptidoglycan
Mucus alone is not the complete defence: protection depends on capture + movement + removal or chemical damage.
A Fibrin Mesh Seals a Breached Barrier
Clotting limits blood loss and closes an entry route for pathogens.
Damaged tissue and activated platelets start a cascade of clotting factors.
The cascade produces thrombin from its inactive precursor.
Thrombin converts soluble fibrinogen into insoluble fibrin.
Fibrin fibres trap platelets and blood cells, forming a clot that dries into a scab.
The clot is not simply a pile of platelets: the fibrin network gives the seal its reinforcing mesh.
Innate Response Buys Time; Adaptive Response Learns the Target
Feature
Innate immunity
Adaptive immunity
onset
rapid
slower on first exposure
recognition
broad pathogen patterns or damage
one antigen specificity per selected clone
main cells here
phagocytes
B and T lymphocytes
memory
no antigen-specific memory
memory cells produce an improved secondary response
The systems cooperate. Innate cells contain infection and present antigens; adaptive cells add precise targeting and long-term memory.
Phagocytes Enclose a Pathogen Before Digesting It
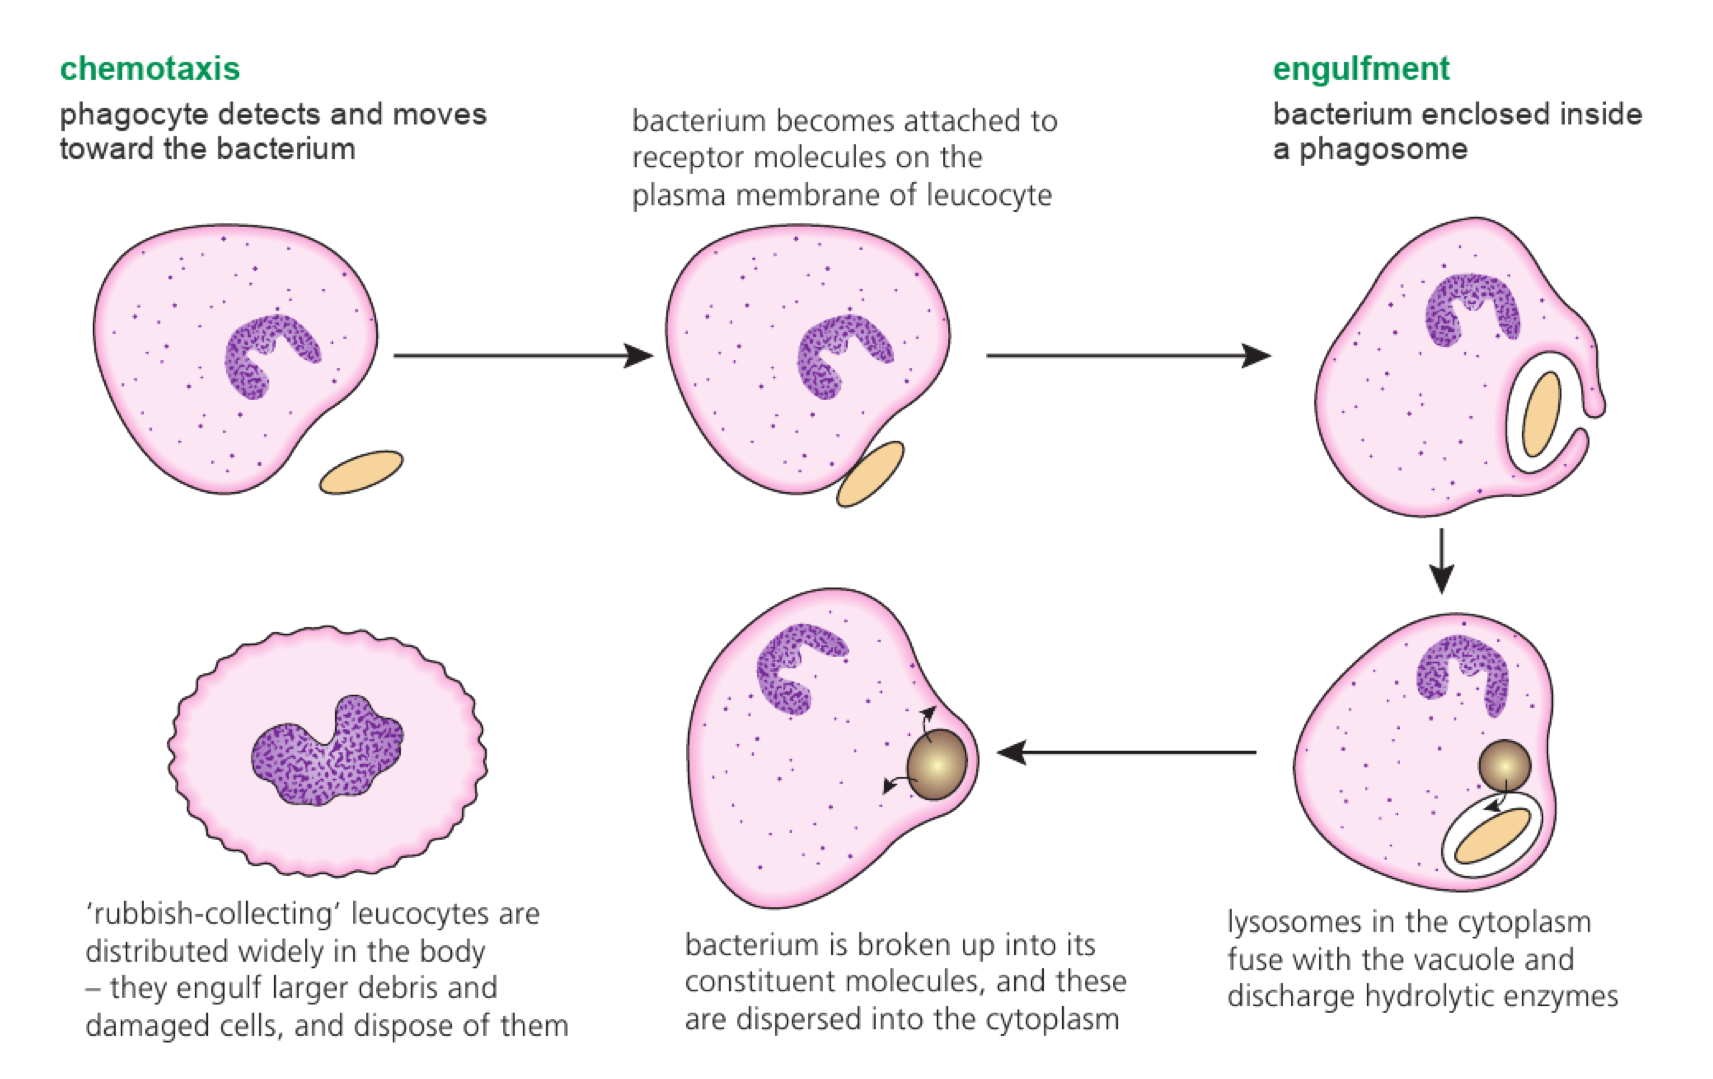
chemical signals → amoeboid movement → receptor attachment → engulfment into a phagosome → lysosome fusion → enzymatic digestion
The pathogen is destroyed inside a membrane-bound vesicle. Lysosomal enzymes are contained, reducing damage to the phagocyte's own cytoplasm.
Lymphocytes Divide the Adaptive Response into Distinct Jobs
All lymphocytes arise from stem cells in bone marrow. B cells mature in bone marrow; T cells mature in the thymus. Mature cells circulate through blood and lymph and concentrate in lymph nodes.
Cell
Core job after activation
helper T cell
coordinates responses and activates matching B cells
killer T cell
destroys infected body cells displaying its antigen
B cell
forms plasma cells and memory B cells
plasma cell
secretes one specific antibody
A resting B cell does not yet release large amounts of antibody; high-output secretion follows activation and differentiation into a plasma cell.
Complementary Binding Makes Recognition Specific
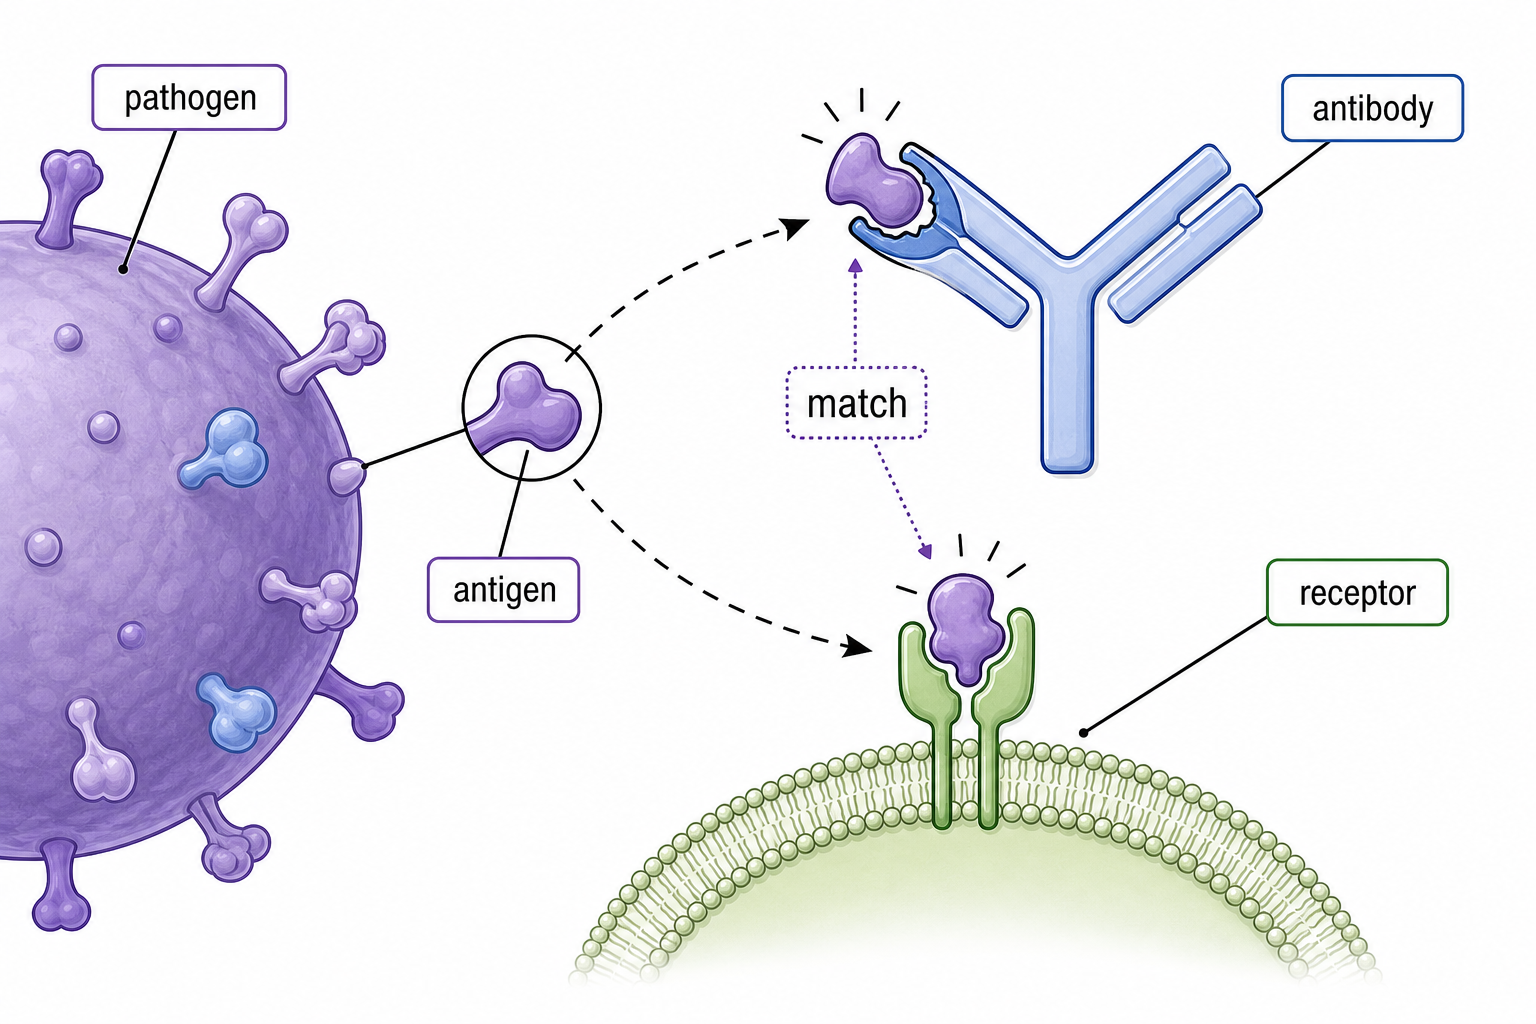
An antigen is a molecular structure recognized specifically by an antibody or lymphocyte receptor and capable of contributing to an immune response. Many are proteins or glycoproteins.
Recognition depends on complementary three-dimensional shape and chemical interactions. One selected lymphocyte clone therefore responds to a particular antigenic feature, not to every foreign molecule.
B-Cell Activation Requires a Matching Helper-T Signal
A B-cell receptor binds its complementary antigen.
The B cell internalizes and digests the antigen.
Antigen fragments are displayed on MHC II proteins.
An activated helper T cell recognizing the same antigen binds and delivers co-stimulation and cytokines.
The B cell is fully activated.
The two linked recognition events act as a specificity check: the B cell captures the target, and a matching helper T cell confirms that response.
Clonal Selection Amplifies One Useful Specificity
An antigen does not instruct a B cell to invent a receptor. It selects the rare pre-existing B cell whose receptor already binds it.
After activation
Result
repeated mitosis
a clone with the same antigen specificity
differentiation into plasma cells
rapid secretion of large amounts of matching antibody
differentiation into memory B cells
long-lived capacity for a faster later response
Plasma cells contain extensive rough endoplasmic reticulum and Golgi apparatus because antibodies are proteins made and exported in large quantities.
Antibodies Mark and Disable Targets Rather Than Killing Cells Themselves
Antibody binding can…
Consequence
cover a toxin or viral attachment site
neutralize its interaction with host cells
cross-link many targets
agglutinate them into easier-to-clear clusters
coat a pathogen
make recognition and engulfment by phagocytes easier
The antibody supplies specific binding. Clearance is then completed by phagocytes, complement and other immune mechanisms.
Memory Changes the Timing and Scale of the Next Response
Response
Starting state
Typical outcome
primary
only rare matching naive cells are present
slower clonal expansion; symptoms may develop
secondary
many long-lived matching memory cells are present
faster, larger response; pathogen may be controlled before disease
Memory cells do not provide a permanent high antibody concentration. They preserve ready-to-expand antigen-specific clones, so re-exposure starts farther along the response pathway.
Defence Is a Layered Route from Exclusion to Memory
keep out with skin and mucosa → seal breaches with fibrin → contain broadly with innate phagocytes → recognize specifically with lymphocytes → amplify selected clones → clear with antibodies and effector cells → remember with long-lived B- and T-cell clones
If this step fails…
The immediate consequence is…
surface barrier
easier pathogen entry
phagocytosis
weaker early containment
helper-T coordination
weaker B-cell and killer-T responses
clonal expansion
too few specific effector cells
memory formation
no improved response on re-exposure
Protection is not one reaction. It is a connected sequence of barriers, broad responses, specific selection and retained memory.
HIV Transmission Requires Both an Infectious Fluid and an Entry Route
Transmission becomes possible when enough HIV in blood, semen, vaginal or rectal fluid, or breast milk reaches susceptible tissue or the bloodstream.
Route
Why transmission can occur
unprotected sexual contact
infected fluid contacts vulnerable mucosa or damaged tissue
shared needles or contaminated blood
virus enters blood directly
pregnancy, birth or breastfeeding
maternal virus can reach the child
HIV is not transmitted by intact-skin contact, sharing food, toilets, coughing, or insect bites. Risk depends on fluid + access + viral load, not on ordinary social contact.
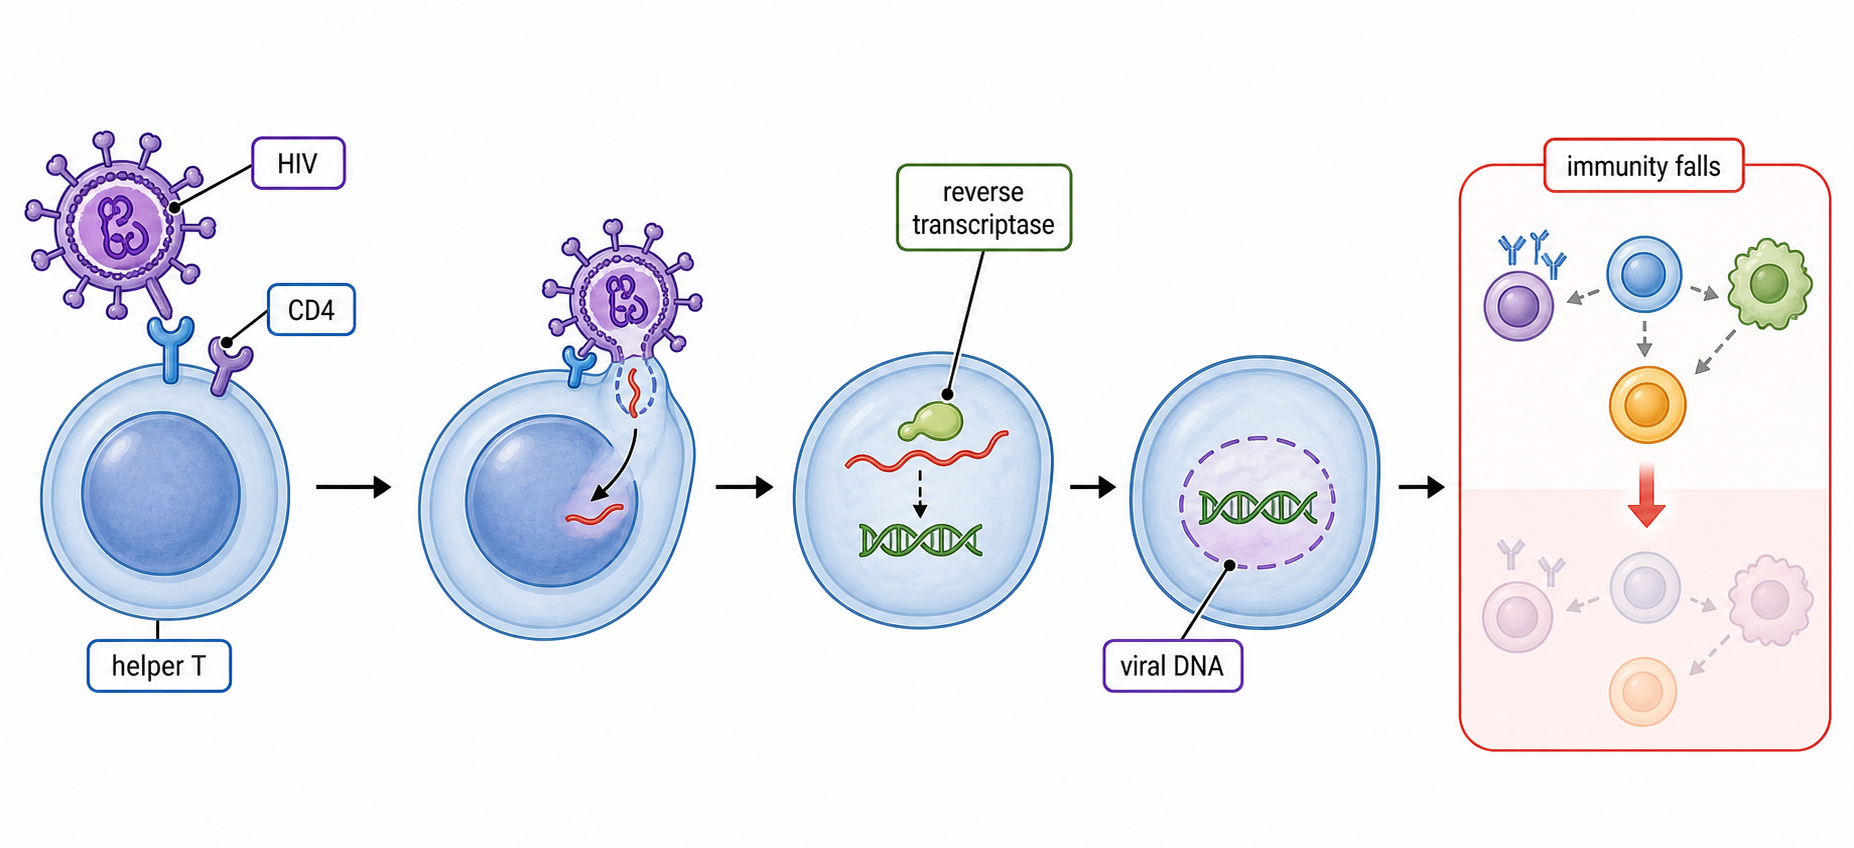
HIV Converts Its RNA into DNA Inside Helper T Cells
attachment to CD4 and co-receptors → entry and uncoating → reverse transcriptase copies viral RNA into DNA → viral DNA integrates into host DNA → host machinery produces new virus
Integration lets viral information persist in the cell. Replication and immune attack progressively reduce functional helper T cells.
AIDS Is the Consequence of Lost Immune Coordination
HIV is the virus. AIDS is an advanced syndrome diagnosed when HIV has caused severe immune damage, indicated by very low CD4 helper-T-cell counts and/or characteristic opportunistic disease.
fewer helper T cells → weaker activation of matching B cells and killer T cells → reduced antibody and cell-mediated responses → normally controlled pathogens and cancers can cause severe disease
A person can transmit HIV without having AIDS. Antiretroviral therapy suppresses viral replication and can prevent or greatly delay progression.
An Antibiotic Works Only If the Pathogen Has Its Target
Selective toxicity means disrupting a bacterial structure or process more than the patient's cells.
Bacterial target
Why it can be selective
peptidoglycan wall synthesis
human cells have no cell wall
70S ribosome function
bacterial ribosomes differ from cytoplasmic human 80S ribosomes
bacterial DNA or metabolic enzymes
key molecules can differ enough for selective inhibition
Viruses have no peptidoglycan wall, ribosomes or independent metabolism. Antibiotics therefore do not treat viral infections; antivirals target stages of viral entry or replication instead.
Antibiotics Select Resistance; They Do Not Create It on Demand
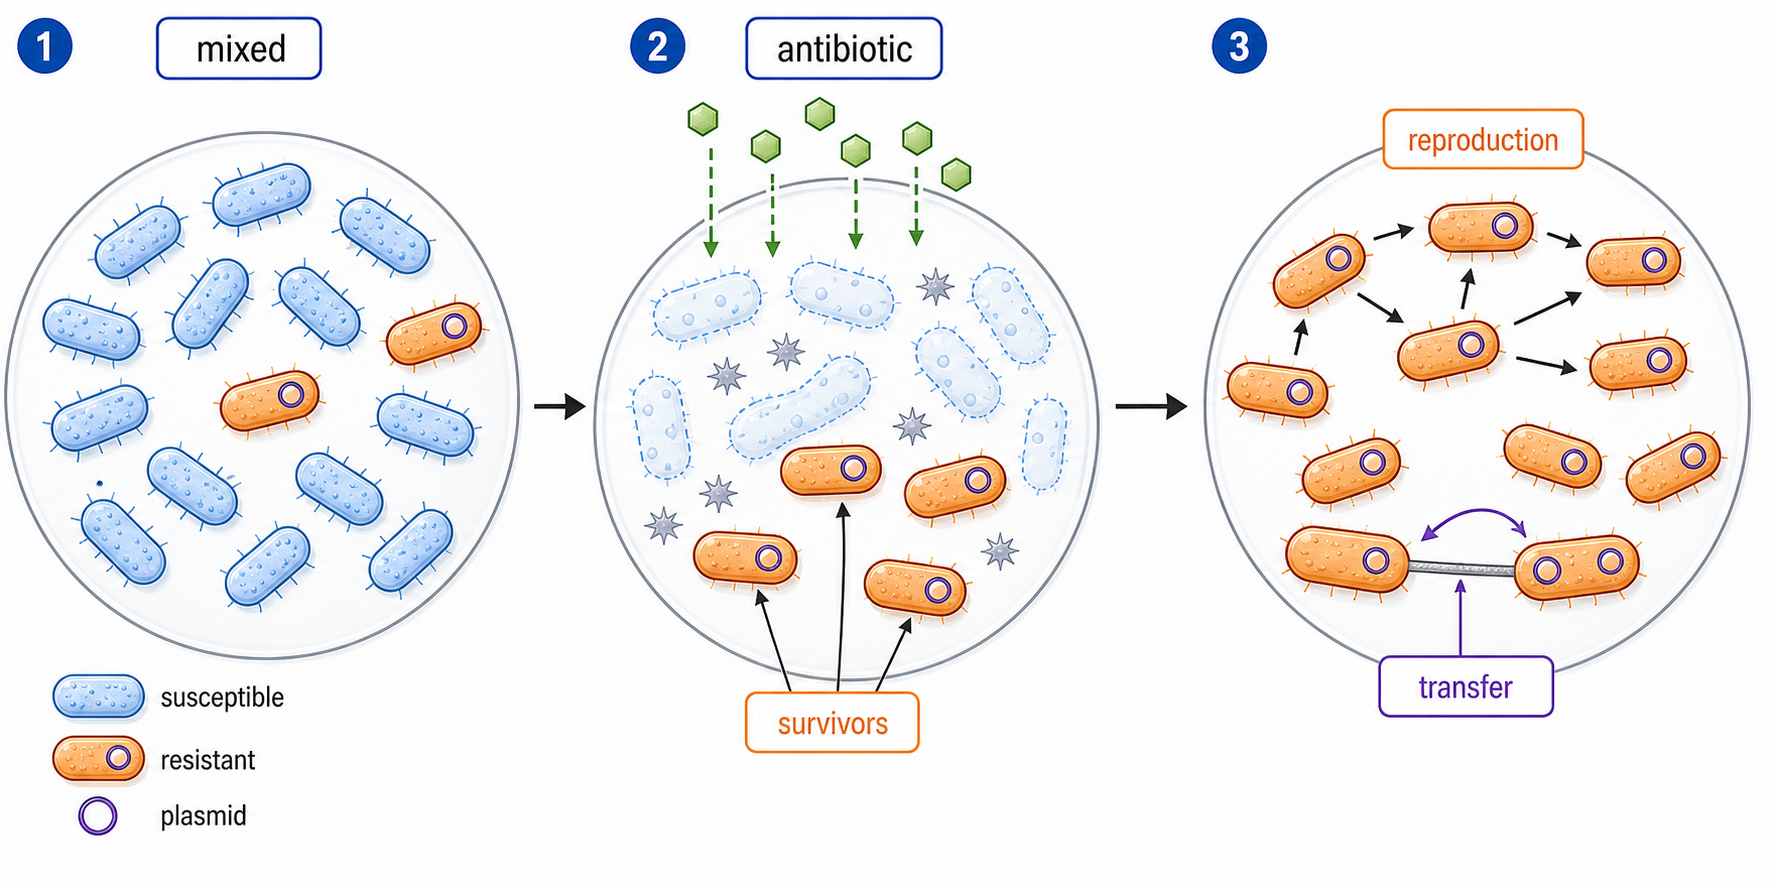
Mutation or acquired DNA creates heritable variation before treatment.
The antibiotic kills or inhibits susceptible bacteria.
Resistant bacteria survive more often.
Survivors reproduce, so resistance alleles become more frequent.
An individual bacterium does not evolve because it ‘tries’ to survive. The population evolves as allele frequencies change across generations.
Multi-Resistance Combines New Alleles, Gene Transfer and Selection
Process
Contribution
mutation
creates a new resistance allele
plasmid transfer
moves resistance genes between bacteria, sometimes across species
reproduction
passes genes to descendants
antibiotic exposure
repeatedly favours carriers of useful resistance genes
Unnecessary prescribing, incorrect doses, poor infection control and routine agricultural use can increase selection or spread. They do not deliberately cause mutation; they make resistant lineages more likely to survive and transmit.
A single bacterium can accumulate several resistance genes, producing a strain for which multiple treatments fail.
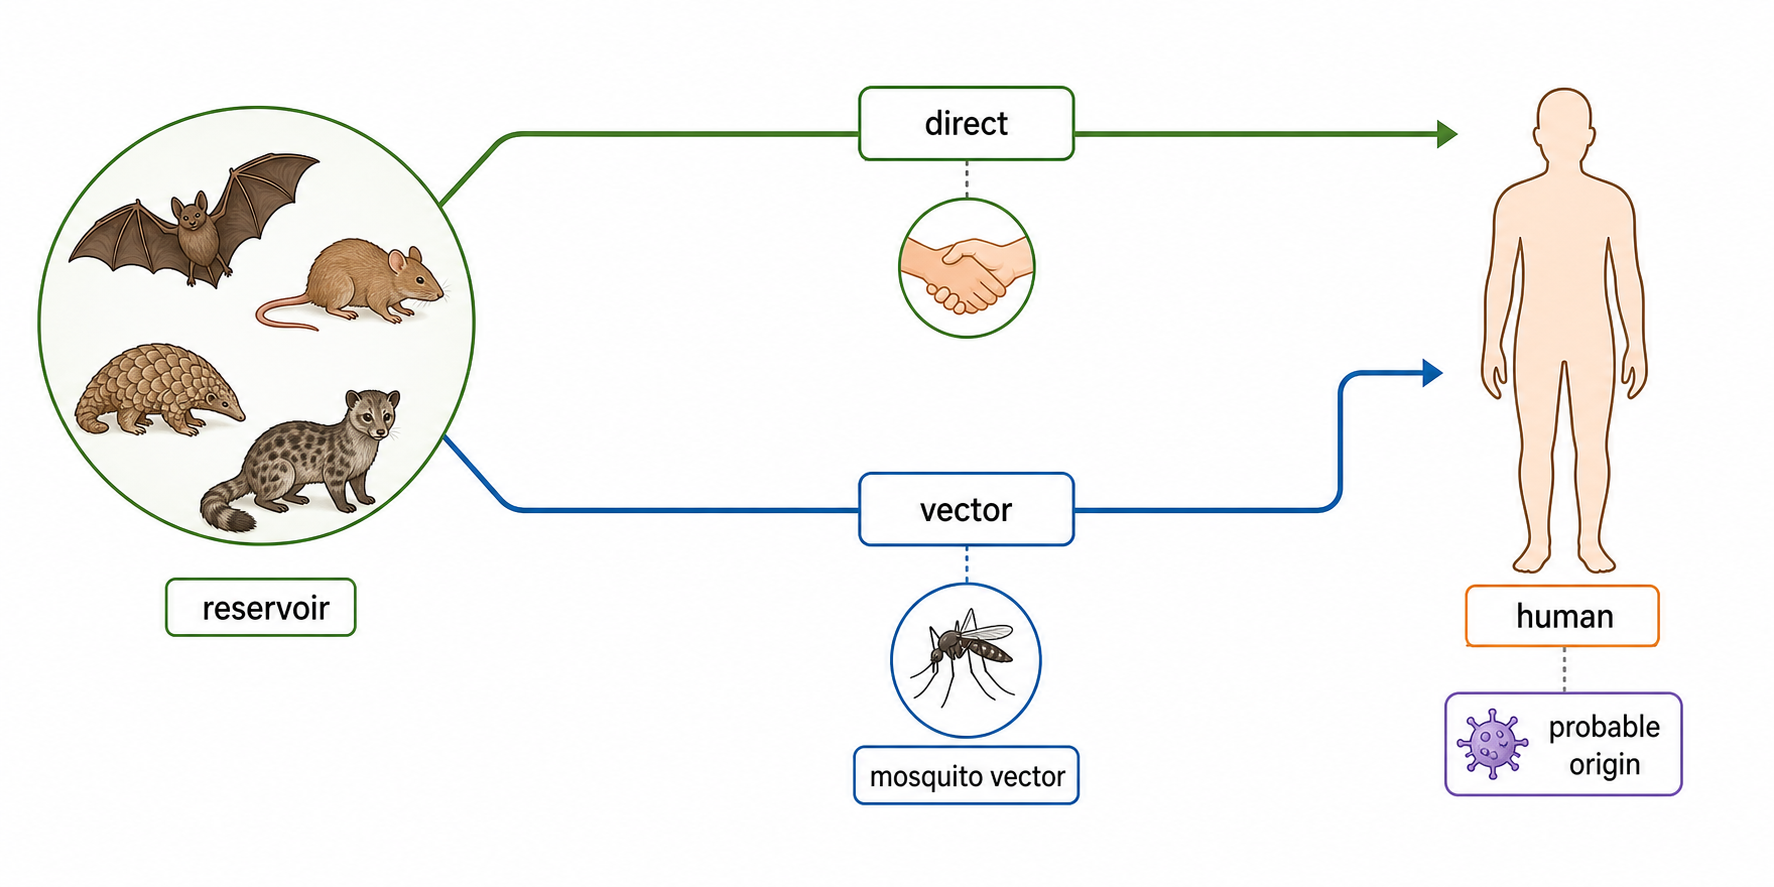
Zoonoses Cross from Animal Reservoirs by Different Routes
Route
Example
direct contact or bite
rabies
food, droplets or close animal exposure
bovine tuberculosis
arthropod vector
Japanese encephalitis via mosquitoes
spillover followed by sustained human transmission
COVID-19, with probable animal origin
A reservoir maintains the pathogen in nature. A vector carries it between hosts. They may be different organisms and should not be used as synonyms.
Different Vaccine Platforms Converge on Antigen Presentation
Platform
What enters the body
How antigen appears
attenuated or inactivated pathogen
whole modified pathogen
its antigens are processed and presented
subunit or toxoid
selected antigenic material
antigen is taken up by antigen-presenting cells
mRNA or DNA vaccine
genetic instructions
host cells make the antigen, then display or release it
All routes aim to activate matching helper T cells, B cells and often killer T cells without the uncontrolled disease caused by the pathogen. Clonal expansion then forms effector and memory cells.
Genetic vaccines do not alter the purpose of the response: they change how antigen is supplied, not the antigen-specific logic of adaptive immunity.
Vaccination Is Active Artificial Immunity
Immunity
Source
Memory formed?
active natural
infection exposes the person to antigen
usually
active artificial
vaccination exposes the person to antigen safely
usually
passive natural
maternal antibodies cross placenta or enter milk
no
passive artificial
prepared antibodies are injected
no
Active means the person's own lymphocytes respond and form memory. Passive means ready-made antibodies arrive from elsewhere, giving immediate but temporary protection.
Vaccination is called artificial because the exposure is deliberately provided—not because the antibodies or memory cells are artificial.
Herd Immunity Works by Breaking Transmission Chains
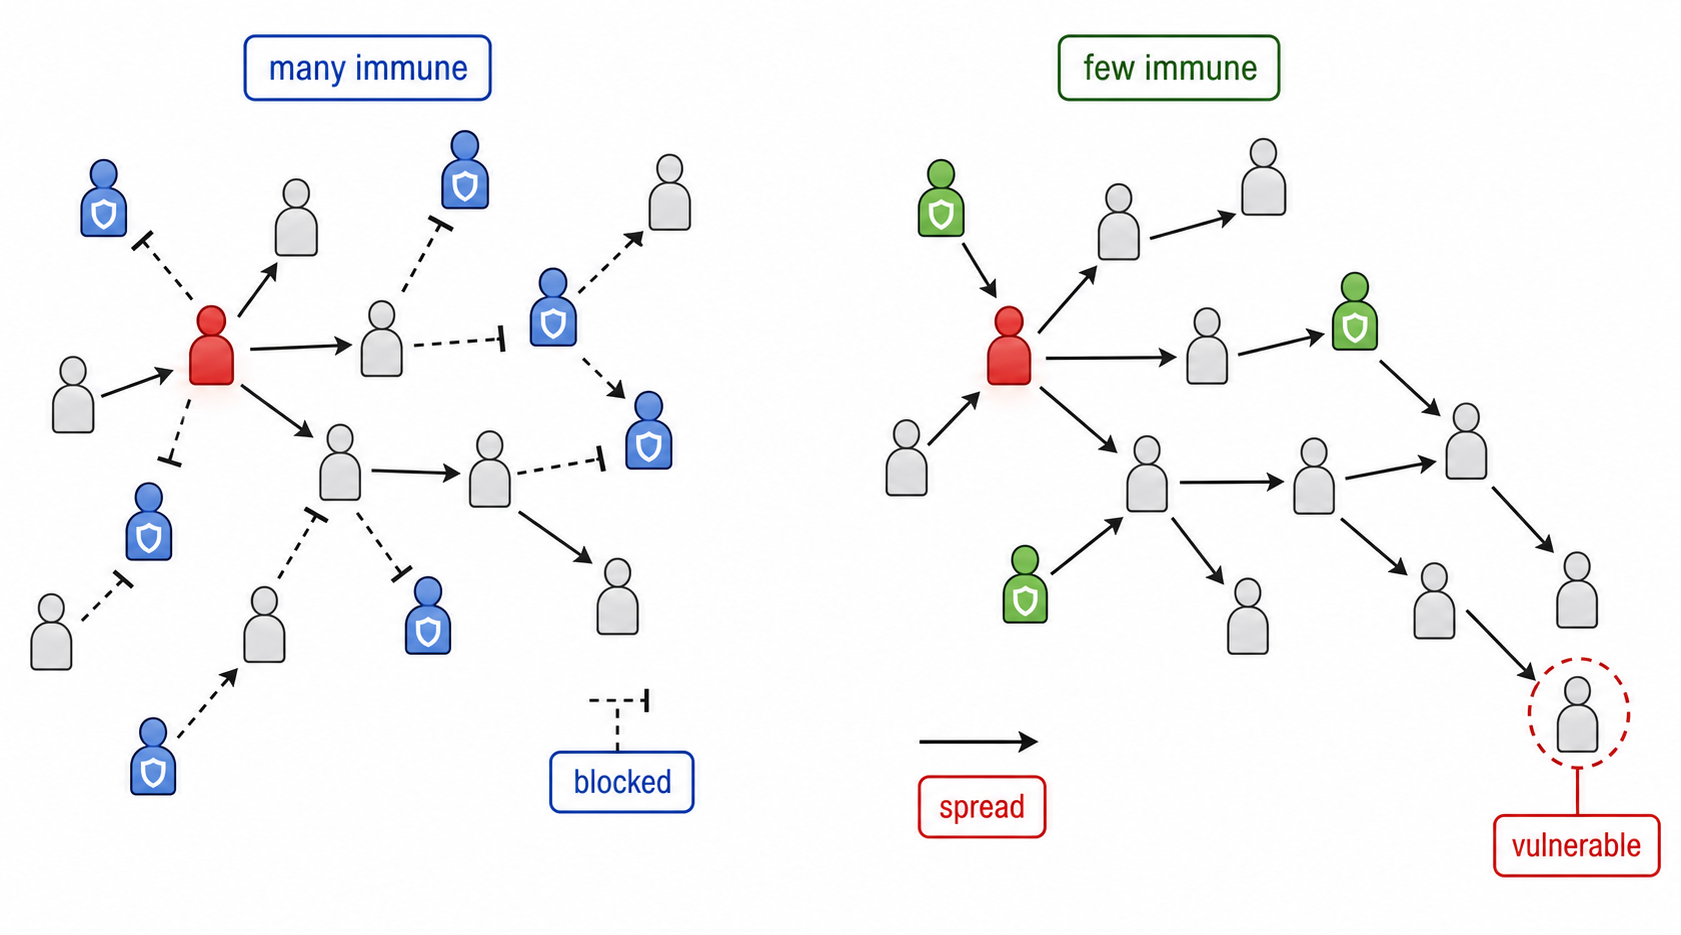
When many people are immune, an infected person is less likely to contact a susceptible person. Transmission chains end more often, indirectly reducing exposure for people who are not immune.
There is no universal threshold. It depends on contagiousness, route of transmission, vaccine effectiveness, duration of immunity, behaviour and how evenly immunity is distributed.
Population protection lowers risk; it does not guarantee that every susceptible individual is safe.
Choose the Measure That Matches the Question
% change=originalnew−original×100
% difference=(A+B)/2∣A−B∣×100
I=PN
VE=IuIu−Iv×100
Question
Measure
How far did one value move from its baseline?
percentage change
How different are two values with no baseline?
percentage difference
How quickly are new cases arising?
incidence
How much lower is incidence in vaccinated people?
vaccine efficacy
Use incidence or risk, not raw case counts, when group sizes or observation time differ. Here, Iᵤ and Iᵥ are incidences in unvaccinated and vaccinated groups.
A Pandemic Comparison Is Only as Fair as Its Denominators
Before comparing groups, check:
the same case definition and testing access
population size or person-time at risk
the same observation period
age, prior infection and health differences
exposure patterns, circulating variants and time since vaccination
uncertainty, missing data and source reliability
Trial arm
Cases
Participants
Risk
unvaccinated
185
15,210
1.216%
vaccinated
11
15,210
0.072%
VE=(1−0.059)×100=94.1%
A correlation or group difference supports a causal claim only when design and confounding have been addressed. Report what the data measure—not more than they can show.
Control Disease by Targeting the Correct Stage
Stage in the disease system
Control logic
reservoir or transmission route
reduce contact, block vectors, use barriers and infection control
pathogen replication
choose a treatment with a real pathogen-specific target
population evolution
use antibiotics only when appropriate and limit spread of resistant strains
susceptible host
vaccinate to build antigen-specific memory before exposure
population network
raise and distribute immunity so transmission chains break
evidence and policy
compare rates fairly, quantify effects and account for confounding
Ask three questions in order: Where is the causal bottleneck? Which intervention acts there? What evidence would show that it worked?
Effective disease control joins cellular mechanisms, evolutionary consequences and population data. A correct intervention aimed at the wrong stage—or supported by an unfair comparison—can still fail.
Pathogens cause infectious diseases
6 marks
Describe the cause, transmission and effects of malaria.
Skin and mucous membranes
3 marks
Describe how disease-causing bacteria are prevented from entering the body.
Blood clotting
7 marks
Explain how blood clotting occurs and the consequence for a person who has hemophilia.
Innate vs. adaptive immune system
1 mark
Distinguish between innate and adaptive immune response.
The graph shows the magnitude of the immune response after infection or after vaccination over time.
Phagocytes exam focus
4 marks
Describe how phagocytic leucocytes may act as a defence against disease.
Lymphocytes exam focus
7 marks
Explain how cells in the bloodstream cause a specific immune response.
Antigens exam focus
1 mark
What is a characteristic of antigens?
B-lymphocyte activation
7 marks
Explain the production of antibodies when a patient is infected with the TB bacterium.
Clones of plasma cells
1 mark
What is a role of activated B cells?
Immunity from memory cells
3 marks
Suggest possible reasons for the observed pattern of presence of antibodies in vaccinated mice.
The summer after vaccination, the prevalence of B. burgdorferi infection in tick nymphs collected on mice from the two sites was measured.
\cline { 2 - 5 } \multicolumn{1}{c|}{}
State of infection of tick nymphs with B. burgdorferi
\cline { 2 - 5 } \multicolumn{1}{c|}{}
Site 1
Site 2
Host mice
Infected
Not infected
Infected
Not infected
Control mice
90
315
57
89
Vaccinated mice
87
288
49
121
HIV transmission
1 mark
How has the transmission of HIV been reduced?
HIV infection and AIDS
4 marks
Discuss the consequences of infection with HIV.
Antibiotics exam focus
3 marks
(i) Estimate the diameter of the zone of inhibition of chloramphenicol. (ii) Distinguish between the action of tetracycline and penicillin on B. subtilis. (iii) Suggest a reason for the result with disc X .
Antibiotic resistance evolution
9 marks
Explain how natural selection can lead to evolution using antibiotic resistance in bacteria as an example.
Zoonoses exam focus
1 mark
State the term used for an infectious disease that can transfer from other species to humans.
Vaccines and immunization
8 marks
Some prokaryotes cause infectious disease in humans. Explain the principles of vaccination.